New OPM Director plus Tuesday’s Tidbits

New OPM Director plus Tuesday’s Tidbits

OPM Headquarters a/k/a the Theodore Roosevelt Building

The Senate narrowly confirmed Kiran Ahuja to be Office of Personnel Management Director this afternoon. Here’s the Senate play by play from the Senate Press Gallery website.

1:37 p.m. Cloture was invoked on the Ahuja nomination, 51-50. Vice President Harris broke the tie.

2:26 p.m. Senator Peters spoke in support of the Ahuja nomination.

2:30 p.m. The Senate began a vote on confirmation of Executive Calendar #107 Kiran Arjandas Ahuja to be Director of the Office of Personnel Management for a term of four years.

3:26 p.m. By a vote of 51-50, the Senate confirmed Executive Calendar #107 Kiran Arjandas Ahuja to be Director of the Office of Personnel Management for a term of 4 years. The Vice President cast the tie breaking vote. 

Here is a link to Ms. Ahuja’s Wikipedia page. Here are links to the Federal Times, Govexec and Federal News Network reports on this event. The FEHBlog wishes Ms. Ahuja good luck.

The Senate Health Education Labor and Pensions Committee held a hearing on COVID-19 vaccination efforts today. Here is a link to the Sen. Patty Murray’s (D Wash) statement on the hearing. Sen. Murray is the Committee chair.

In this regard, the Wall Street Journal reports that

The White House said the U.S. will fall short of President Biden’s goal for 70% of the adult population to receive at least one coronavirus vaccine dose by July 4.

Mr. Biden had set the goal in early May, with an aim for a return to normalcy to mark the Independence Day holiday. White House Covid-19 coordinator Jeffrey Zients said Tuesday the target had been met for those age 30 and over but not for the overall eligible population.

Mr. Zients said it would take a few extra weeks to reach the president’s target and cited a reluctance to get the vaccine among people between the ages of 18 and 26 as one of the challenges facing the country.

“The reality is many younger Americans have felt like Covid-19 is not something that impacts them and they have been less eager to get the shot,” Mr. Zients said.

On Thursday, June 24, at 10 am, the Financial Services and General Government Subcommittee of the House Appropriations Committee will markup the fiscal year 2022 appropriations bill that includes OPM and FEHB appropriations. Here’s a link to a Fedweek article on the markup.

STAT News offers a couple of sobering articles, one on antibiotic resistance and the other on health equity concerns

  • According to a new STAT Report an estimated 700,000 people die annually from antimicrobial resistance, a number that could rise to 10 million by 2050, according to a World Health Organization report issued in 2019. In the U.S. alone, there are more than 2.8 million antibiotic-resistant infections and 35,000 deaths from those infections each year, according to data from the Centers for Disease Control and Prevention. A number of issues have fueled resistance and stunted development of new antibiotics. And while there are various efforts underway to address those challenges, creating incentives to change the trajectory of antibiotic resistance takes commitment and imagination. There are several experiments under way that aim to spur development of new products while still ensuring profit. In the U.K. and Sweden, pilot programs are testing a pull incentive, which involves a subscription-style business model in which a government offers upfront payments to drug makers in exchange for unlimited access to their antibiotics. The idea is to enable drug companies to recover their costs and make an appropriate profit without having to sell large volumes of antibiotics. Last week, U.S. lawmakers re-introduced legislation to create a similar mechanism.
  • [Researchers have identified]232 counties in the mainland U.S. where men aged 49 and under are at unusually high risk of dying from colorectal cancer, according to a study published last year in the American Journal of Cancer Research. The researchers also found that compared with white men, Black men in these hot spots who have colorectal cancer are more likely to be diagnosed with advanced stages of the disease and less likely to survive it. * * * [S]ince the 1990s, even as colorectal cancer rates have declined for people 50 and older, they have more than doubled among American adults under 50, according to the National Cancer Institute. By 2030, predicts a study published in April, colorectal cancer will be the leading cause of cancer-related deaths in people aged 20 to 49. The reason behind the rise remains a mystery. “We don’t know where this is coming from,” said Charles R. Rogers, an assistant professor of public health at the University of Utah School of Medicine and lead author of the hot spots study. “Just like we don’t really know why Black people have the highest chance of getting and dying from it.” The article explains how researches like Professor Rogers are shedding light on the cause of this inequity by studying the hot spots, among other things.

In brighter Tuesday Tidbits

  • The Patient Centered Outcomes Research Institute funded by health plan premiums is seeking public comment on its national health priorities. The public comment period runs from June 28 through August 27.
  • Fierce Healthcare reports that “Five Blues plans are teaming up to invest in a new pharmacy solutions venture called Evio. Blue Cross Blue Shield of Massachusetts, Blue Cross Blue Shield of Michigan, Blue Shield of California, Highmark Health and Independence Blue Cross are backing Evio, according to an announcement released Tuesday. The new company aims to establish outcomes-based arrangements with drugmakers, especially for high-cost therapies. In addition, Evio aims to collect and provide real-world evidence for medications to ensure the right product is getting to the right patient.” Makes sense to the FEHBlog.
  • Fierce Healthcare also informs us that “Amazon Web Services wants to help incubate early-stage digital health companies that can collaborate with the tech giant’s healthcare customers and partners. Amazon’s cloud division launched a healthcare accelerator to boost startups’ growth in cloud technologies and enable early-stage companies to tap into AWS’ technical and commercial expertise. The program will focus on technologies such as remote patient monitoring, data analytics, patient engagement, voice technology and virtual care, according to a blog post from Sandy Carter, vice president of worldwide public sector partners and programs at AWS.”

Monday Roundup

Photo by Sven Read on Unsplash

The International Foundation of Employee Benefit Plans informs us that

The Department of Labor’s (DOL) Employee Benefits Security Administration along with the Office of Personnel Management, Internal Revenue Service, Department of the Treasury, Centers for Medicare & Medicaid Services, and Department of Health and Human Services (collectively, The Departments) issued an information collection related to certain reporting requirements under section 204 of Title II of Division BB of the Consolidated Appropriations Act, 2021 (CAA) that are applicable to group health plans and health insurance issuers offering group or individual health insurance coverage.​

In addition, the Departments and OPM are also seeking input about whether the requirements apply to Federal Employees Health Benefits carriers, including whether or not they are also health insurance issuers.

Here’s the FEHBlog’s input on that last point. Congress extended specific provisions of Division BB of the Consolidated Appropriations Act, 2021 to the FEHB Program when it created a new Section 8902(p) of the FEHB Act. Today’s notice concedes that Section 204 was not among those provisions in Section 8902(p). Regulations are intended to implement and interpret statutory law, and in the case of the FEHBP there is no statute to implement here. What’s more carriers already are obligated to report aggregated prescription benefit data to OPM. In other words, the regulatory field is occupied as far as the FEHB Program is concerned. The public comment deadline on this information collection notice is July 23, 2021.

The American Hospital Association gleefully reports

Nearly 100 bipartisan House members led by Reps. Thomas Suozzi, D-N.Y., and Brad Wenstrup, R-Ohio, urge the departments of Health and Human Services, Labor and the Treasury [in a June 17, 2021 letter] to ensure their rulemaking for the No Surprises Act reflects congressional intent for a balanced process to settle payment disputes between health plans and providers. The lawmakers also emphasized the need to provide sufficient time for public comments and evaluation through proposed notice and comment rulemaking. 

The FEHBlog wonders what caused Congress to fire this shot across the regulator’s bow. The statutory deadline for these rules is October 1, 2021, thereby creating an all too brief three month long implementation period for providers, payers, lawyers and arbitrators. This should be interesting.

To show that the FEHBlog is not entirely cranky as he writes this post, CVS Health announced today

Over the last year, Aetna, a CVS Health® company, has been implementing a comprehensive strategy to reduce suicide attempts 20 percent among Aetna members by the year 2025. With the right intervention and support, resources and management of suicidal thoughts, suicide is known to be preventable. In fact, 90 percent of people who die by suicide have a potentially treatable mental health condition.

This month, Aetna is launching its latest initiative — the development of a specialty provider network with a sole focus on suicide prevention in collaboration with Psych Hub, the world’s most comprehensive platform for mental health education. The joint effort will further arm Aetna practitioners with no-cost, evidence-based instruction, tools, and resources to identify and treat those at risk of suicide.

Well done and best of luck.

Also from the COVID-19 front Bloomberg informs us

After more than a year of obsessively tracking Covid-19 case numbers, epidemiologists are starting to shift focus to other measures as the next stage of the pandemic emerges.

With rich countries vaccinating growing proportions of their vulnerable populations, the link between infection numbers and deaths appears to be diminishing. Now, in some places the focus is on learning to live with the virus — and on the data that matter most to avoid fresh lockdowns.

“It’s possible we’ll get to a stage of only monitoring hospitalizations,” said Jennifer Nuzzo, an epidemiologist at Johns Hopkins University’s Coronavirus Resource Center, which has built one of the most comprehensive platforms to track the virus and its impact.

The Wall Street Journal provides an overview of the COVID-19 variant called Delta.

The latest data from The Centers for Disease Control and Prevention estimates the Delta variant makes up 9.9% of reported U.S. Covid-19 cases, while Alpha stands at 65.5%. * * *

Scientists are still studying the virus and their early conclusions aren’t definitive. But British scientists, who have probably done the most work on the variant, estimate it is from 40% to as much as 80% more infectious than the so-called Alpha variant, or B.1.1.7, which was first identified in England last year, is now prevalent in the U.S. and is itself more contagious than the version of the virus that emerged in China in 2019.

An analysis of more than 14,000 Delta cases by England’s public-health agency found a double dose of the shot developed by Pfizer Inc. and BioNTech SE reduces the risk of hospitalization after infection with Delta by 96%. Two doses of the vaccine developed by the University of Oxford and AstraZeneca reduce the risk by 92%, Public Health England said.

Very few of those hospitalized in the U.K. have been fully vaccinated, with the new cases mostly among younger people who aren’t yet vaccinated. There is no evidence that young adults and children are more at risk proportionately from this variant than other age groups, and the increased transmission mostly reflects the fact that they haven’t been immunized, scientists say.

In other news that caught the FEHBlog’s eye this Monday —

  • The FEHBlog enjoys following the healthcare efforts of business giants like Amazon, Apple, and Walmart. ZdNet reports on Microsoft’s new healthcare strategy.
  • Louisville KY television station WDRB tells us

Brentwood, Tenn.-based LifePoint Health [a large regional health system that owns over 80 hospitals] will acquire Louisville-based Kindred Healthcare LLC, a specialty hospital company, for undisclosed terms, according to a news release Monday. The deal is scheduled to close by the end of the year. The announcement comes weeks after Louisville-based Humana Inc. said it would absorb the remainder of the former Kindred’s home health and hospice business. In the news release, LifePoint said it plans to continue Kindred’s strategy of growing by establishing joint ventures and partnerships with hospitals. * * * LifePoint said it plans to invest $1.5 billion in its business following the deal.

At the time of wrapping up this post on Monday evening, the Senate had not yet taken up Kiran Ahuja’s nomination to be OPM Director. The FEHBlog will keep an eye on this matter. [Tuesday morning supplement — The Senate Press Gallery Calendar informs us that

The Senate on Tuesday morning at 11:45 am will hold two votes:

  1. Confirmation of the Fonzone nomination.
  2. Motion to invoke cloture on Kiran Ahuja to be Director of the Office of Personnel Management.

The Senate will recess following the cloture vote on the Ahuja nomination until 2:15 p.m. 

At 2:30 p.m. vote:

  1. Confirmation of the Ahuja nomination.

Weekend update

Thanks to Alexandr Hovhannisyan for sharing their work on Unsplash.

Happy Fathers’ Day and First Day of Summer.

Both Houses of Congress remain in session for Committee business and floor voting this week. Among the scheduled hearings for this week, the Senate Health Education Labor and Pensions Committee will hold a hearing on Tuesday morning to “examine vaccines, focusing on America’s shot at ending the COVID-19 pandemic.”

Speaking of which, Kaiser Health News reports on a June 10, 2021, FDA advisory committee meeting on pediatric COVID-19 vaccines. Here’s a link to the FDA’s briefing document.

Amy Howe who writes on the U.S. Supreme Court discusses the decisions that the Court is expected to issue over the remainder of this month and possibly early July. There are many interesting issues at stake but none of them relate to the FEHB Program.

STAT News offers an encouraging op-ed from two physicians who think that the pandemic has caused people to be more engaged with their healthcare. Hope springs eternal.

Friday Stats and More

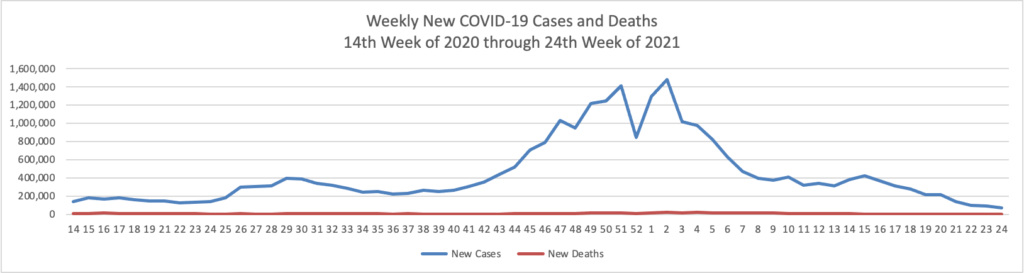
Based on the Centers for Disease Control’s COVID-19 Data Tracker website, here is the FEHBlog’s chart of new weekly COVID-19 cases and deaths over the 14th week of 2020 through 24th week of this year (beginning April 2, 2020, and ending June 16, 2021; using Thursday as the first day of the week in order to facilitate this weekly update):

and here is the CDC’s latest overall weekly hospitalization rate chart for COVID-19:

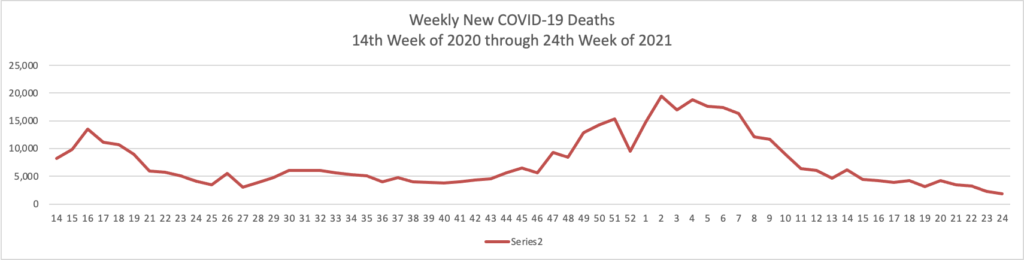
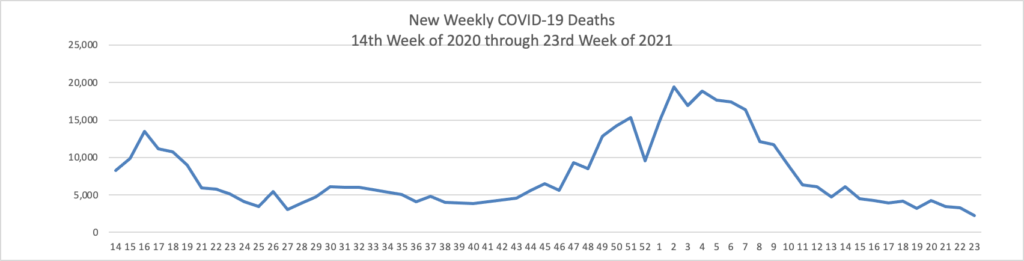
The FEHBlog has noticed that the new cases and deaths chart shows a flat line for new weekly deaths because new cases materially exceed new deaths. Accordingly here is a chart of new COVID-19 deaths over the period (April 2, 2020, through June 16, 2021):

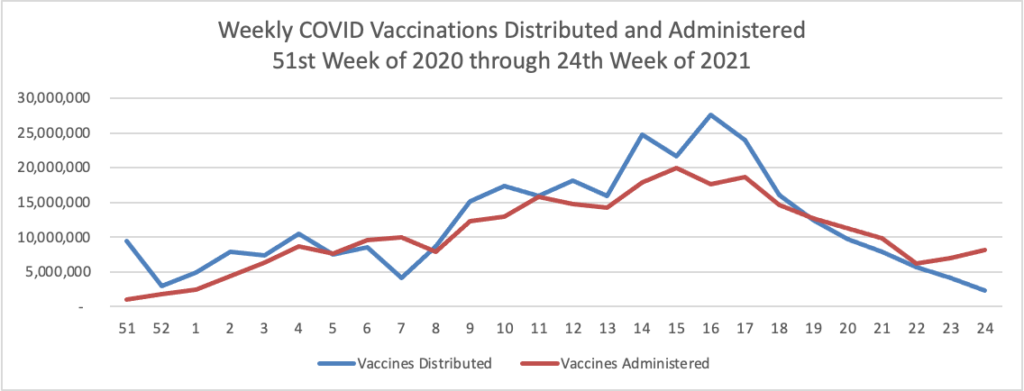
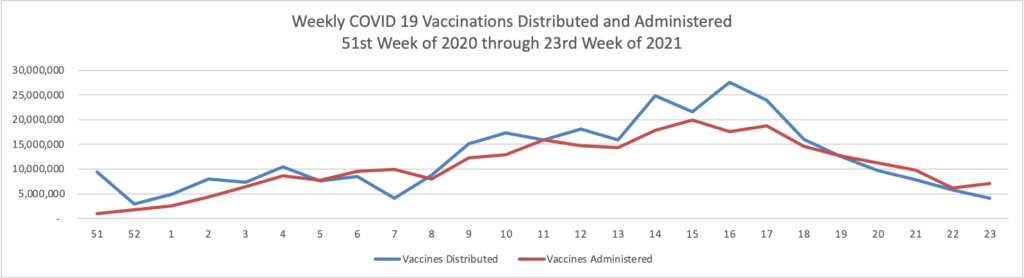
Finally here is a COVID-19 vaccinations chart over the period December 17, 2020, through June 16, 2021 (six months) which also uses Thursday as the first day of the week:

Bloomberg reports that

President Joe Biden urged unvaccinated Americans to get inoculated from coronavirus, warning that the highly transmissible delta variant of the virus could cause more deaths. “Even while we are making incredible progress [as reflected above], it remains a serious and deadly threat,” Biden said Friday during a White House event to celebrate 300 million doses of vaccine administered during the first 150 days of his administration.“The data is clear: If you are unvaccinated, you’re at risk of getting seriously ill, or dying, or spreading it.” A large swath of Americans — particularly in the politically conservative South — have declined shots despite warnings from health authorities that the virus remains a threat.”

in other COVID-19 news

  • Medscape informs us that “While the investigation into cases of myocarditis possibly associated with COVID vaccines proceeds, the American Heart Association (AHA)/American Stroke Association (ASA) continue to urge everyone who is eligible for the vaccine to get it without delay. ‘We remain confident that the benefits of vaccination far exceed the very unusual risks,’ the leadership of the AHA/ASA said in a statement issued June 12. ‘The risks of COVID-19 infection include its potentially fatal consequences and the potential long-term health effects that are still revealing themselves, including lingering consequences affecting the heart, brain, vascular system, and other organs after infection,’ they point out. Late last week, the Centers for Disease Control and Prevention (CDC) alerted healthcare providers that the COVID-19 Vaccine Safety Technical Work Group (VaST) of the Advisory Committee on Immunization Practices (ACIP) will meet June 18 to review cases of myocarditis reported in adolescents and young adults after they received a COVID-19 vaccine manufactured by Pfizer–BioNTech or Moderna.
  • MedPage Today reports that “During the American Medical Association (AMA) House of Delegates annual meeting, members debated whether natural immunity or previous infection with SARS-CoV-2 was sufficient for the merit of immunity credentials.” The House of Delegate voted against treating natural immunity as equivalent to vaccination. “Multiple delegates pointed out that using natural immunity in lieu of vaccination would pit the AMA’s recommendations against those of the CDC.” Nevertheless as the Mayo Clinic points out, natural immunity helps us achieve some level of herd immunity. It needs to be considered with vaccinations for that purpose.

If you want more details on yesterday’s Affordable Care Act decision from the U.S. Supreme Court, check out Prof. Katie Keith’s post in the Health Affairs blog.

Beckers Hospital News lists seven Fortune 500 health insurers by membership. Health Payer Intelligence discusses the latest sustainability report from the company that tops this list, UnitedHealth Group.

On this Juneteenth holiday, Fierce Health tells us about how “healthcare executives call on President Biden to take ‘innovative, bold’ steps to tackle health equity using AI, big data.”

“It’s not a lack of data—we have so much data in this country now, in our healthcare systems and our EHRs and our patient registration systems,” Cole said. “The data is there but the analytics capability of that—what to do with that data—is something that we’re continuing to work on every day.”

Cole and John Lumpkin, M.D., president of the Blue Cross and Blue Shield of North Carolina Foundation, said both of their organizations have been reworking their collection and organization of race, ethnicity, gender identity and other related data tied to health inequity—a change that “should be a very simple thing to do” but requires an internal data system overhaul, Lumpkin said.

Still, executives said the finish line of those efforts is worthwhile. Incorporating SDOH data can yield substantial health and costs benefits at the individual and population levels, they said.

The Wall Street Journal reports on the rising fortunes of the country’s major pharmacy chains, CVS Health and Walgreens.

In health system merger news —

  • Healthcare Dive informs us that “Beaumont Health and Spectrum Health are looking to merge in a deal that would result in Michigan’s biggest health system with 22 hospitals and 64,000 employees across the state, with combined annual revenue of almost $13 billion. Executives of the two systems announced Thursday they have signed a letter of intent to explore creating a joint health system. The deal would include Spectrum’s Michigan-based health insurance plan, Priority Health, which has 1.2 million customers.”
  • Fierce Healthcare reports that “Southern health systems Ochsner Health and Rush Health Systems have announced plans for a merger they expect to be completed about halfway through 2022. The deal follows a 2019 strategic partnership between the two nonprofit providers and comes hot on the heels of Louisiana-based Ochsner’s merger with Lafayette General Health, which closed in October 2020 and grew the system to 35 hospitals. Rush, which has seven hospitals and more than 30 clinics in eastern Mississippi and western Alabama, will be rebranded as Ochsner Rush Health should the merger receive regulatory approval.”
  • Healthcare Dive also tells us that “Tenet, a major U.S. health system, has agreed to sell five hospitals in the Miami-Dade area for $1.1 billion to Steward Health Care System, a physician-owned hospital operator and health network. The deal also includes the hospitals’ associated physician practices. Dallas-based Steward has agreed to continue using Tenet’s revenue cycle management firm, Conifer Health Solutions, following the completion of the deal, which is expected to close in the third quarter. Further underscoring Tenet’s strategic focus, the sale will not include Tenet’s ambulatory surgery centers in Florida. Tenet will hold onto those assets as its ambulatory business becomes a bigger focus for the legacy hospital operator.”

Thursday Miscellany

U.S. Supreme Court building, Wash. DC

At long last, the U.S. Supreme Court issued its opinion today in the third case reaching the Court on the issue of the constitutionality of the Affordable Care Act (“ACA”). In an opinion written by Justice Breyer and joined by the Chief Justice and four other Justices, the Court ruled in short as follows:

As originally enacted in 2010, the Patient Protection and Affordable Care Act required most Americans to obtain minimum essential health insurance coverage. The Act also imposed a monetary penalty, scaled according to in- come, upon individuals who failed to do so. In 2017, Con- gress effectively nullified the penalty by setting its amount at $0. See Tax Cuts and Jobs Act of 2017, Pub. L. 115–97, §11081, 131 Stat. 2092 (codified in 26 U. S. C. §5000A(c)).

Texas and 17 other States brought this lawsuit against the United States and federal officials. They were later joined by two individuals (Neill Hurley and John Nantz). The plaintiffs claim that without the penalty the Act’s minimum essential coverage requirement is unconstitutional. Specifically, they say neither the Commerce Clause nor the  Tax Clause (nor any other enumerated power) grants Congress the power to enact it. See U. S. Const., Art. I, §8. They also argue that the minimum essential coverage re- quirement is not severable from the rest of the Act. Hence, they believe the Act as a whole is invalid. * * *

[W]e conclude that the plaintiffs in this suit failed to show a concrete, particularized injury fairly traceable to the defendants’ conduct in enforcing the specific statutory provision they attack as unconstitutional. They have failed to show that they have standing to attack as unconstitutional the Act’s minimum essential coverage provision. Therefore, we reverse the Fifth Circuit’s judgment in respect to standing, vacate the judgment, and remand the case with instructions to dismiss.

Justice Thomas filed a concurring opinion, and Justice Alito, joined by Justice Gorsuch, filed a dissenting opinion. The FEHBlog confidently can state that he predicted this favorable outcome for the ACA. It always has been clear to the FEHBlog that the Supreme Court took the case to kill the lawsuit, not the law.

The Senate will take up Kiran Ahuja’s nomination to be OPM Director when it resumes floor business on Monday June 21. If Ms. Ahuja’s nomination is not confirmed next week, the Senate will be away from our Nation’s capital for two weeks for the Independence Day holiday.

Reg Jones’ latest column in FedWeek concerns federal employee survivor benefits in the case of a post-retirement marriage.

In federal employment news, Federal News Network reports that President Joe Biden signed the Juneteenth National Independence Day Act this afternoon, establishing June 19 as a federal holiday. Most federal employees will have tomorrow, June 18 off for observance as June 19 falls on a Saturday this year, the Office of Personnel Management said. * * * Nearly every state already recognizes Juneteenth as a holiday, but it now becomes the first federal holiday created since Martin Luther King Jr. Day was established in 1983.”

In COVID-19 news and this should come as no surprise, Medscape informs us that “More than half of unvaccinated Americans would prefer to get a COVID-19 vaccination at their doctors’ office, according to the results of a new national survey. * * * The preference to be vaccinated in a medical office was three to five times higher among unvaccinated Americans than were other strategies such as vaccinations at retail pharmacies or drug stores, community health centers, public health clinics, drive-up clinics, and large public vaccination sites.” As of today, 65% of Americans over age 18, and 87% of Americans over age 65, have had at least one dose of a COVID-19 vaccination.

In a burst of closing miscellany —

  • Kaiser Health News tells us that ” The pandemic-caused recession and a federal requirement that states keep Medicaid beneficiaries enrolled until the national emergency ends swelled the pool of people in the program by more than 9 million over the past year, according to a report released Thursday. The latest figures show Medicaid enrollment grew from 71.3 million in February 2020, when the pandemic was beginning in the U.S., to 80.5 million in January, according to a KFF analysis of federal data.”
  • Health Payer Intelligence informs us that “Medicare Advantage plans may better address racial care disparities than fee-for-service Medicare, according to the second in a series of reports that ATI Advisory has prepared for Better Medicare Alliance (BMA) in 2021. “With over 26.5 million beneficiaries enrolled in Medicare Advantage today, this report shows that minority beneficiaries are a driving force behind these enrollment gains; turning to Medicare Advantage to meet their health and social needs. When policymakers stand up for Medicare Advantage, they stand up for these seniors, too,” Allyson Y. Schwartz, president and chief executive officer of the Better Medicare Alliance, said in the press release. Around half of all Black Medicare beneficiaries and 53 percent of Latinx Medicare beneficiaries are in a Medicare Advantage plan, the report found. In contrast, only 34 percent of White beneficiaries and 31 percent of those who identified as “Other” races were enrolled in a Medicare Advantage plan.”
  • STAT News reports that “ovarian cancer, which kills about 15,000 Americans every year, has historically been one of the thornier cancers to treat. Only in the last few years has a new class of potent drugs, called PARP inhibitors, started to change that. But even with these promising new treatments, too often, tenacious tumors come roaring back. So there’s a need for yet newer drugs that can overcome any resistance the cancer evolves. According to research published Thursday, scientists might have found one. And it’s not actually a new drug at all. In fact, it’s been sitting, retired, in a drug library for decades. “While evaluating mechanisms of PARP inhibitor resistance over the last few years we came across this drug, novobiocin, which curiously enough, is an antibiotic,” said Alan D’Andrea, director of the Susan F. Smith Center for Women’s Cancers at the Dana-Farber Cancer Institute and co-author of the new study.” Encouraging.
  • “The U.S. Food and Drug Administration today approved a nasal antihistamine for nonprescription use through a process called a partial prescription to nonprescription switch. The FDA approved Astepro (azelastine hydrochloride nasal spray, 0.15%) for seasonal and perennial allergic rhinitis—commonly known as allergies—for adults and children six years of age and older.  ‘Seasonal and perennial allergies affect millions of Americans every year, causing them to experience symptoms of nasal congestion, runny nose, sneezing and more,” said Theresa M. Michele, M.D., director of the office of nonprescription drugs in the FDA’s Center for Drug Evaluation and Research. “Today’s approval provides individuals an option for a safe and effective nasal antihistamine without requiring the assistance of a healthcare provider.’”

Midweek Update

Photo by Dane Deaner on Unsplash

The Senate took no action on Kiran Ahuja’s nomination to be OPM Director today as Senators Booker and Peters remain out of pocket due to family illnesses.

On the hospital front —

  • The Advisory Board informs us about U.S. News and World Reports most recent rankings of children’s hospitals.
  • Axios reports that “Some of the hospitals with the highest revenue in the country also have some of the highest prices, charging an average of 10 times more than the actual cost of the care they deliver, according to new research by Johns Hopkins University provided exclusively to Axios.”

On the mental healthcare front, we have two articles on start- up companies from Katie Jennings in Forbes. One concerns Burlingame, Calif.-based Lyra Health and the other concerns “Lifestance Health Group, one of the nation’s largest outpatient mental health providers.” Check them out.

On the prescription drug front —

  • Healthcare Dive reports that “Anthem, one of the biggest U.S. payers, has joined an initiative to create low-cost generic drugs for hospital and retail pharmacies. The initiative CivicaScript, a subsidiary of hospital-owned nonprofit drugmaker Civica Rx, plans to initially develop and manufacture six to 10 common but pricey generic medicines that don’t have enough market competition to drive down cost, officials said Wednesday. The first generics could be available as early as 2022.”
  • Fierce Pharma informs us that “Antibody treatments have shown little success in helping COVID-19 patients with  severe disease. But a large [UK] study of hospitalized patients reveals that Regeneron’s antibody cocktail can reduce the chance of death in patients who haven’t produced their own antibody responses to the disease.”
  • STAT News interviews the Alzheimer Association’s CEO about the newly approved drug Aduhelm.

In miscellaneous news

  • The Wall Street Journal reports “Apple Inc. Chief Executive Tim Cook has said the company’s greatest contribution to mankind will be in health. So far, some Apple initiatives aimed at broadly disrupting the healthcare sector have struggled to gain traction, according to people familiar with them and documents reviewed by The Wall Street Journal.”
  • Healthcare Dive tells us that “A University of Pennsylvania study that tracked Medicare claims for about 1.35 million beneficiaries who had joint replacement surgery found that hospitals participating in bundled payment programs spent less on the hip and knee joint procedures than hospitals receiving traditional fee-for-service payments. Spending, however, did not differ between hospitals that voluntarily joined bundling programs and those whose involvement was mandatory, according to the findings, which were published in a JAMA research letter. The results failed to validate assumptions that voluntary participants tend to achieve greater savings because they choose programs for the opportunity to reduce spending. The findings come as the head of the Center for Medicare and Medicaid Innovation, Elizabeth Fowler, suggested the agency would look to shift away from voluntary arrangements in favor of more mandatory models.”
  • Fierce Healthcare informs us that “The Centers for Disease Control and Prevention (CDC) released new interim guidance late Monday for healthcare providers treating patients with post-COVID conditions—an umbrella term the agency is using to capture a wide range of physical and mental health issues that sometimes persist four or more weeks after an individual’s COVID-19 infection. Sometimes referred to as “long COVID,” the conditions can present among COVID-19 patients regardless of whether they were symptomatic during their acute infection, the agency wrote in the guidance.”

Tuesday’s Tidbits

Photo by Patrick Fore on Unsplash

The Senate Press Gallery informs us from today’s proceedings

12:22 p.m. Majority Leader Schumer announced that due to Senators Booker and Peters having family illnesses the cloture vote on the Ahuja nomination [to be OPM director] is delayed; and moved the Senate to a period of morning business.

It looks like the Majority Leader is concerned about a close vote. The FEHBlog will continue tracking and best wishes to the Booker and Peters families for speedy recoveries.

Federal Times reports that “Federal employees can enroll, re-enroll or change their flexible spending account coverage during the month of June, as the Office of Personnel Management announced June 14 that it authorized a special enrollment period as part of provisions outlined in the Consolidated Appropriations Act and the American Rescue Plan.”

The Federal Times adds

Because the Consolidated Appropriations Act authorized unlimited carryover of FSA funds for 2020 and 2021, feds that didn’t re-enroll in an FSA plan for 2021 but had remaining money left in their accounts in 2020 may wish to use the special enrollment period to reopen their accounts and gain access to those carried over funds.

The new flexibilities for the 2020 and 2021 plan years also allow enrollees with dependents who would have normally aged out of the program to continue to use those funds until the child is 14, rather than 13, and the government approved hand sanitizer and masks as FSA medical expenses.

In the tidbits department

  • STAT News informs us that “Amazon has made its FDA-cleared Covid-19 test available to consumers online, alongside a consumer diagnostics website where people can view their results. The consumer diagnostics website, AmazonDx.com, was previously only available to Amazon employees. As of Tuesday, however, it appears any customer can sign into the site using the same login information they use to access the shopping portion of the tech giant’s website.  Amazon received FDA authorization for the at-home test kit in May.”
  • Fierce Healthcare tells us that “A JAMA Internal Medicine study is the latest in a string of analyses revealing hospitals’ frequent noncompliance with a new federal mandate requiring them to post prices for medical services. Published Monday, the study found that, as of early March, 83 out of 100 randomly sampled hospitals were noncompliant with at least one of the major requirements of a new rule from the Centers for Medicare & Medicaid Services (CMS). This decreased slightly to 75 in a parallel review of the country’s 100 highest-revenue hospitals.
  • Healthcare Dive reports that “Humana is acquiring home-based services provider One Homecare Solutions from a private equity firm to beef up its at-home care offerings, as a growing number of payers foray into direct medical delivery. The acquisition of Miramar, Florida-based One Homecare, which does business as Onehome, follows Humana’s decision to snap up home health giant Kindred at Home for $5.7 billion and is meant to boost the insurer’s value-based home health strategy. Financial terms of the deal, expected to close in the second quarter of this year, were not disclosed.”
  • Healthcare Dive also reports that About half of physicians and even more patients said the U.S. healthcare system discriminates against people a great deal, a good amount or somewhat, according to a survey out Tuesday from the nonpartisan research group NORC at the University of Chicago. Patients’ trust in their primary doctor rises with age and income, though 12% of respondents said they have been discriminated against by a healthcare facility, and Black patients were twice as likely to report being discriminated against than White patients, the report found. But 81% of physicians gave their employers either an A or B grade for their efforts to address health equity, and said they’re optimistic their system will improve diversity and equity in the next five years.
  • Health Payer Intelligence discusses “six expectations employers have for provider care coordination Employers are looking for greater price transparency, reduced overtreatment, and improved patient experience, and overall better care coordination from their provider partners.”
  • The Wall Street Journal reports that “A national charity will for the first time buy medical debt, totaling $278 million, directly from hospitals, a push to speed financial relief to patients, many of whom shouldn’t have been billed at all under the hospitals’ financial-aid policies. RIP Medical Debt, which uses donations to wipe out unpaid medical bills, has reached a deal with nonprofit Ballad Health, a dominant hospital system in Tennessee and Virginia, to buy debt owed by 82,000 low-income patients. Many likely qualified for free care under Ballad’s policy but didn’t get it, executives at Ballad involved in the agreement said. The patients lacked applications, they said. RIP Medical Debt will abolish the total amount and is expected to notify households of the debt relief this month. Some bills are 10 years old.” Bravo.

In the OPM rule making agenda department, here are three more found in last Friday’s semi-annual regulatory agenda.

  • OPM is engaged in joint rule making with HHS to implement a provision of Consolidated Appropriations Act Division BB that Congress did not apply to the FEHB. “This joint rule with HHS would implement the prescription drug reporting requirements that apply to group health plans and health insurance issuers offering coverage in the group and individual markets under section 204 of the No Surprises Act.” OPM already has created aggregated pharmacy data reporting requirements for FEHB carriers.
  • OPM is engaged in joint rule making with HHS on the provider non-discrimination provision of the ACA Section 2706. While this law does apply to the FEHB, it’s unusual that OPM is teaming up with HHS to craft the rule.
  • OPM is engaged in a joint rule making with HHS on reporting requirements related to air ambulance and agent and broker services and HHS enforcement provisions under Division BB of the CAA 2021. OPM does need to create rules on air ambulance reporting related to the No Surprises Act.

Friday Stats and More

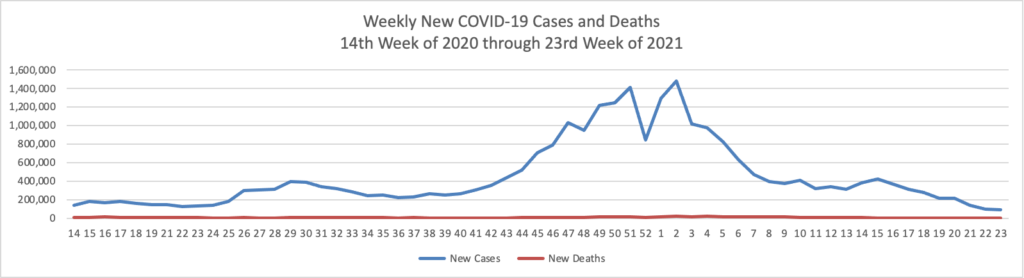
Based on the Centers for Disease Control’s COVID-19 Data Tracker website, here is the FEHBlog’s chart of new weekly COVID-19 cases and deaths over the 14th week of 2020 through 23rd week of this year (beginning April 2, 2020, and ending June 9, 2021; using Thursday as the first day of the week in order to facilitate this weekly update):

and here is the CDC’s latest overall weekly hospitalization rate chart for COVID-19:

The FEHBlog has noticed that the new cases and deaths chart shows a flat line for new weekly deaths  because new cases significantly exceed new deaths. Accordingly here is a chart of new COVID-19 deaths over the period (April 2, 2020, through June 9, 2020):

Finally here is a COVID-19 vaccinations chart over the period December 17, 2020, through June 9, 2021, which also uses Thursday as the first day of the week:

All signs continue to look up. 50% of the American population over 12 years old is fully vaccinated per the CDC.

In COVID-19 news, the Food and Drug Administration announced the latest actions stemming from its ongoing investigation of the problematic Emergent Biosolutions Baltimore factory that had been manufacturing the Johnson & Johnson one dose COVID-19 vaccine:

[The FDA] is authorizing for use, under the emergency use authorization (EUA) for the Janssen COVID-19 vaccine, two batches of vaccine drug substance manufactured at the Emergent BioSolutions facility in Baltimore. Before making this decision, the FDA conducted a thorough review of facility records and the results of quality testing performed by the manufacturer. Based on this review and considering the current COVID-19 public health emergency, the FDA concluded these batches are suitable for use. While the FDA is not yet ready to include the Emergent BioSolutions plant in the Janssen EUA as an authorized manufacturing facility, the agency continues to work through issues there with Janssen and Emergent BioSolutions management. * * *

The FDA has determined several other batches are not suitable for use, but additional batches are still under review and the agency will keep the public informed as those reviews are completed.

Per Fierce Healthcare, the New York Times is reporting that the unsuitable batches total 60 million vaccine doses. Yikes.

HR DIve reports

Most employers “no longer need to take steps to protect their workers from COVID-19 exposure in any workplace, or well-defined portions of a workplace, where all employees are fully vaccinated,” the Occupational Safety and Health Administration said in guidance updated Thursday.

The agency also published an emergency temporary standard for U.S. healthcare employers. Employers included in the emergency temporary standard’s definition must develop and implement a plan to protect employees from COVID-19 in the workplace, and they must designate one or more workplace COVID-19 safety coordinators to implement and monitor their plans. The document also lays out requirements for patient screening and management, personal protective equipment and physical distancing, among other subjects.

OSHA’s updated guidance for all industries, meanwhile, encourages employers to grant paid time off for employees to get vaccinated. Employers also should implement physical distancing for unvaccinated and other at-risk workers in communal work areas, including limiting the number of such workers in one place at any given time.

In other healthcare news

  • Precision Vaccines informs us about an Avalere Heath study finding that non-COVID immunizations among adolescents and adults were significant down last year.
  • The American Medical Association discusses five ways healthcare must change for the post-pandemic world.
  • Becker’s Hospital Review tells us that

Cleveland Clinic, IBM, Aetna and Anthem have partnered to form a blockchain health firm, called Avaneer Health.

The Chicago-based healthcare company will aim to use blockchain capabilities to make healthcare more efficient and reduce administrative costs, according to a June 9 news release.

Five things to know:

Avaneer Health will be formed as a standalone business with significant investments from its founders: Aetna, Anthem, Cleveland Clinic, Health Care Service Corporation, IBM, The PNC Financial Services and Norfolk, Va.-based Sentara Healthcare.

Avaneer Health is a member-based open network supporting utilities developed for the healthcare industry. It is expected to improve healthcare by removing administrative barriers and alleviate inefficiencies in cross-party transactions that slow down care delivery.

The incoming CEO will be Stuart Hanson, former managing director and senior healthcare industry executive at JPMorgan Chase. He will take the helm in August.

The company will be built on blockchain technology to ensure privacy and reduce costs of data exchange.

Finally, the Biden Administration released its Spring 2021 semi-annual regulatory agenda.

The Unified Agenda provides uniform reporting of data on regulatory and deregulatory activities under development throughout the Federal Government, covering approximately 60 departments, agencies, and commissions. Each edition of the Unified Agenda includes regulatory agendas from all Federal entities that currently have regulations under development or review. Agencies of the United States Congress are not included. Fall editions of the Unified Agenda include The The Regulatory Plan, which presents agency statements of regulatory priorities and additional information about the most significant regulatory activities planned for the coming year. 

The FEHBlog will be discussing the OPM agenda in next week’s posts.

In this week’s Econtalk podcast episode, the host Russ Roberts holds a conversation with author Ian Leslie about his book Conflicted. “Leslie argues that, far from being a negative thing, conflict is often the essential ingredient that helps us get to the right answer or best solution. Because some of our best thinking comes in collaboration with others, learning how to disagree civilly when our views conflict is the key to productive conversation in business and in marriage.” Outstanding.

Thursday Miscellany

Photo by Juliane Liebermann on Unsplash

From the COVID-19 front

  • Sobering news from the Wall Street Journal that “It took less than six months for the globe to record more than 1.88 million Covid-19 deaths this year, according to a Wall Street Journal analysis of data collected by Johns Hopkins University. The university’s count for 2021 edged just ahead of the 2020 death toll on Thursday. These numbers underscore how unevenly the pandemic spread around the globe, often hitting poorer nations later, but before they had access to the vaccines that have benefited Europe and the U.S. * * * Vastly different vaccination rates have sharpened the global divide. Only 2% of people in Africa and just over 6% in Asia have received at least one dose of vaccine, according to Our World in Data. That compares with 22% in South America, more than 40% in the European Union and more than half in the U.S. * * * World leaders are due to discuss their response to the pandemic when they gather in Cornwall, in southwestern England, on Friday.” David Leonhardt sheds light on the vaccinating the world in the New York Times. The bottom line is as he points out: “A rapid global vaccination program — combined with natural immunity in people who have already had Covid — could create the same virtuous cycle that’s underway in the U.S., Britain and other countries: A decline in cases feeds on itself, as there are fewer infected people able to spread the virus to others. And by prioritizing older people for shots, countries can cause deaths to decline even more sharply than cases.”
  • To that end, here in the U.S., Moderna “has requested an emergency use authorization (EUA) for its [two dose, mRNA] COVID-19 vaccine in adolescents [ages 12-17] with the U.S. Food and Drug Administration (FDA). Pfizer’s two dose, mRNA vaccine already is being administered to adolescents in this age group.
  • Johnson & Johnson announced that “the U.S. Food & Drug Administration (FDA) has authorized an extension of the shelf life for the Johnson & Johnson single-shot COVID-19 vaccine from 3 months to 4.5 months.” Absent this science based extension, large surplus of unused doses of this vaccine would have begun to expire later this month.  The Wall Street Journal adds that the federal government continues to suspend shipments of new doses of the single dose vaccine, evidently to allow the surplus to deplete.
  • Fierce Healthcare reports on Kaiser Permanente’s efforts to boost the COVID-19 vaccination numbers. As of today, 64% of Americans over age 18 have received at least one dose and over 75% of Americans over age 65 are fully vaccinated.

In big healthcare legal news, a friend of the FEHBlog pointed out to him today that yesterday the Department of Health and Human Services submitted its interim final rule on No Surprise Billing Act implementation rule to the Office of Management and Budget’s Office of Information and Regulatory Affairs for final review before publication in the Federal Register.

AGENCY: HHS-CMS RIN: 0938-AU63Status: Pending Review
TITLE:Requirements Related to Surprise Billing; Part I (CMS-9909)
STAGE: Interim Final Rule ECONOMICALLY SIGNIFICANT: Yes 
RECEIVED DATE: 06/08/2021LEGAL DEADLINE: Statutory  

In other healthcare and healthcare business news:

  • Healthcare Dive informs us that “UnitedHealthcare, the biggest private payer in the U.S., is delaying a controversial policy that could retroactively deny emergency room bills it deems non-emergent — potentially saddling patients with costly medical bills — following intense backlash from patient advocates and hospital groups. ‘Based on feedback from our provider partners and discussions with medical societies, we have decided to delay the implementation of our emergency department policy until at least the end of the national public health emergency period,’ UnitedHealthcare tweeted on Thursday.
  • Health Payer Intelligence identifies four payers that have embraced value based contracting with healthcare providers in the first half of 2021.
  • STAT News reports on what’s ahead for Biogen’s new Alzheimer’s Disease drug. The article concludes “Despite the controversies, Mark Miller, the former executive director of the Medicare Payment Advisory Commission, thinks Aduhelm will be widely used and make billions for Biogen. Infusion centers used for cancer patients and others can accommodate Aduhelm patients, said Miller, now the executive vice president at the Arnold Ventures philanthropy. Doctors will make good money providing the drug. Most Medicare patients have supplemental coverage that will pick up the 20 percent copay. ‘There’s not a lot of friction here to say, “Don’t do this,’ he said.”
  • STAT News also tells us that “The treatment known as CAR-T, in which white blood cells are genetically modified to attack blood cancer, is one of the most exciting and expensive in medicine. But it has not been directly compared to standard treatments in a randomized trial — until now. Bristol Myers Squibb said Thursday that its CAR-T, Breyanzi, prevented the return of large B-cell lymphoma better than the standard of care treatment, which includes a chemotherapy regimen and a stem cell transplant, in which bone marrow cells are replaced to try to cure blood cancer. The news was released in a terse press release that does not include any details about how the therapy performed. But if the results hold up when published in a medical journal or presented at a medical meeting, they would represent a big step forward for CAR-T therapy.”
  • The American Medical Association offers a blueprint for controlling blood pressure.
  • NIH Director Dr. Francis Collins in his blog interviews U.S. Surgeon General Vivek Murthy on fighting the ongoing opioid epidemic.

In federal employment news, Federal News Network reports that

The Biden administration has lifted the 25% occupancy limit at federal buildings, though agencies must still jump through several hoops before bringing more employees back for in-person work.

The Office of Management and Budget, along with the Office of Personnel Management and General Services Administration, on Thursday issued detailed guidance on the administration’s approach for reopening agency offices during the pandemic — and offered a highly-anticipated glimpse at their approach for telework, remote work and other workforce flexibilities in a post-pandemic world.

Midweek Update

Mark Gongloff in Bloomberg opinion lays out the global COVID-19 situation quite clearly

Former FDA chief Scott Gottlieb, a sensible observer throughout this disaster, tells Michael R. Strain he sees Covid-19 becoming like the flu, both in its seasonality and fatality rate. He figures Americans will be fully back to work and school by the fall and then face a new Covid wave in the winter. But with widespread vaccinations, it shouldn’t be worse than a bad flu season. Sounds kind of nice. 

But in the developing world, vaccinations are lagging badly, giving the disease too many chances to evolve. The scariness of India’s “delta” variant may be overhyped, but it seems both more transmissible and severe than others, writes Sam Fazeli. Vaccines are effective against it. But it could make Covid more tiger-like again for unvaccinated Americans and Brits, including young people.

So developed countries must get far more serious about vaccinating the rest of the world to stem further deaths, mutations and economic damage. President Joe Biden promising to give the world 500 million Pfizer doses is a great start, but it’s only a start. 

Former U.K. Prime Minister Gordon Brown writes this Friday’s G-7 meeting is a chance for countries to commit to more such concrete action and spending. The world’s biggest countries must pony up to the best of their ability, as they have with other emergencies. 

Also from the COVID-19 front

  • The Centers for Medicare and Medicaid Services announced today that

While many Medicare beneficiaries can receive a COVID-19 vaccine at a retail pharmacy, their physician’s office, or a mass vaccination site, some beneficiaries have great difficulty leaving their homes or face a taxing effort getting around their communities easily to access vaccination in these settings. To better serve this group, Medicare is incentivizing providers and will pay an additional $35 per dose for COVID-19 vaccine administration in a beneficiary’s home, increasing the total payment amount for at-home vaccination from approximately $40 to approximately $75 per vaccine dose. For a two-dose vaccine, this results in a total payment of approximately $150 for the administration of both doses, or approximately $70 more than the current rate.

  • The Department of Health and Human Services announced that

The U.S. government will procure approximately 1.7 million courses of an investigational antiviral treatment, molnupiravir (MK-4482), for COVID-19 from Merck, pending emergency use authorization (EUA) or approval from the U.S. Food and Drug Administration (FDA).

Molnupiravir (MK-4482) is designed to induce viral genome copying errors to prevent the virus from replicating in the human body, and evidence to date from clinical trials in patients with COVID-19 suggests that molnupiravir may reduce replication of the SAR-CoV-2 virus.

This treatment is being evaluated in an ongoing Phase 3 trial for its potential to reduce the risk of hospitalization or death in non-hospitalized patients who have symptoms for five days or less and are at high risk for severe illness. The trial plans to enroll a total of 1,850 patients globally with final data expected in the fall of 2021.

  • FedSmith offers more details on Blue Cross Federal Employee Program (FEP)’s announcement that it will offer a $50 wellness incentive to FEP members over age 18 who are fully vaccinated against COVID-19. Notably, “FedSmith has been advised that eligible members who have already been vaccinated for COVID-19 can also take advantage of this program and receive the $50 on their MyBlue Wellness Card. These individuals will also have to submit evidence of their COVID-19 vaccination record.”

From the general healthcare front

  • PriceWaterhouseCoopers (PwC) released its Health Research Institute’s 2022 projection of medical cost trend.

PwC’s Health Research Institute (HRI) is projecting a 6.5% medical cost trend in 2022, slightly lower than the 7% medical cost trend in 2021 and slightly higher than it was between 2016 and 2020. Healthcare spending is expected to return to pre-pandemic baselines with some adjustments to account for the pandemic’s persistent effects.

HRI defines medical cost trend as the projected percentage increase in the cost to treat patients from one year to the next, assuming benefits remain the same. Typically, spending data from the prior year is used as an input in the projection. For 2021 and 2022, the medical cost trend is the projected percentage increase over the prior year’s spending, with the effects of the pandemic removed from the prior year’s spending.

  • Not surprisingly, the American Hospital Association sent a letter to UnitedHealthcare stating in pertinent part that

America’s hospitals and health systems are deeply concerned by UnitedHealthcare’s (UHC) recent policy announcement [recently mentioned in the FEHBlog] to allow for the retroactive denial of coverage for emergency-level care in facilities. This policy would put patients’ health and wellbeing in jeopardy, and we urge you to reverse the policy immediately.

The AHA contends that UHC’s policy violates the Affordable Care Act’s requirement that heath plans adjudicate emergency care claims using a prudent layperson standards. The FEHBlog expects that UHC has taken this legal requirement into account. The FEHBlog will continue to follow this matter.

  • mHealth Intelligence reports that “New research out of the University of California Davis finds that telehealth treatments for people with non-urgent mental health needs can be delivered via an asynchronous (store-and-forward) platform just as well as through an audio-visual platform.” This approach could make the delivery of mental healthcare more efficient.
  • According to a company press release, “Datavant, the leader in helping healthcare organizations securely connect their data, and Ciox Health, the leader in clinical data exchange, today announced that they have signed a definitive agreement to merge the two companies in a transaction valued at $7.0 billion. The combined entity, to be named Datavant, will be the nation’s largest health data ecosystem, enabling patients, providers, payers, health data analytics companies, patient-facing applications, government agencies, and life science companies to securely exchange their patient-level data. “The fragmentation of health data is one of the single greatest challenges facing the healthcare system today,” said Pete McCabe, CEO of Ciox Health. “Each of us has many dozens of interactions with the healthcare system over the course of our lives, and that information is retained in siloed databases across disparate institutions. Every informed patient decision and every major analytical question in healthcare requires the ability to pull that information from across the health data ecosystem while protecting patient privacy. We are thrilled to join forces with the Datavant team to connect health data to improve patient outcomes. Together we are well positioned to navigate the technical, operational, legal, and regulatory challenges to doing so, and are committed to acting as a neutral connectivity solution for our many customers and partners.”
  • The National Committee for Quality Assurance answers questions about the use of electronic clinical data in HEDIS reporting. For example,

Q: How does administrative reporting relate to ECDS reporting?

A: Administrative claims are considered a key data source for ECDS reporting if the data can also be made available to a member’s care team. It is one of the four major data categories for ECDS reporting. The ECDS reporting method expands the types of data permitted for HEDIS® reporting by allowing the use of structured data from electronic health records, health information exchanges and clinical registries, and case management systems in addition to administrative claims.

Q: Is NCQA going to phase out the hybrid method of data collection from HEDIS?

A: NCQA is actively assessing the appropriateness of removing the hybrid reporting method from select HEDIS measures as other data sources improve.