Tuesday’s Tidbits

Tuesday’s Tidbits

Photo by Patrick Fore on Unsplash

From the COVID-19 front

  • The Hill informs us that “President Biden on Tuesday pleaded with Americans to get vaccinated against COVID-19 as the White House signaled a shift toward grassroots tactics to reach those who have yet to get a shot.” Here is a link to the President’s full remarks.
  • NPR Shots offers a daily look at each state’s progress in vaccinating its residents.

From the hospital pricing transparency front —

  • The Wall Street Journal explains how it has been analyzing the pricing data that federal law required hospitals to make publicly available on January 1, 2021. “The Journal reviewed hospital pricing disclosures collected by Turquoise Health Co., a startup that has been gathering the data from hospital websites since the regulations went into effect.” The Turquoise Health website is worth a gander.
  • NPR Shots also analyzed the newly available hospital pricing data. “While it’s still an unanswered question about whether price transparency will lead to overall lower prices, KHN took a dive into the initial trove of data to see what it reveals. Here are five takeaways from the newly public data and tips for how you might be able to use it to your benefit: 1) As expected prices are all over the map; 2. Patients can look up information but the info is incomplete; 3. Third party firms like Turquoise Health are trying to make searching prices simpler and cash in; 4. Consumers can use the data to negotiate with hospitals when paying cash, and 5. Hospitals are not fully on board currently.

In the tidbits department —

  • Today, the Centers for Medicare and Medicaid Services announced Dr. Meena Seshamani, M.D., Ph.D. [formerly with MedStar Health] as Deputy Administrator and Director of Center for Medicare. She started her work today.
  • Fierce Healthcare reports “The United Health Foundation, the philanthropic arm of the UnitedHealth Group, released its America’s Health Rankings Health Disparities Report last week, and the healthcare giant found a number of disparities worsened in the 2017 to 2019 time frame. While the data come from before the pandemic, experts say they offer a baseline that can be used to address critical public health needs. For example, adults who did not graduate high school had a rate of frequent mental distress that was 123% higher than people with a college degree. Females had a 70% higher rate of depression than males, according to the report.”
  • NPR Shots discusses how an “obesity drug’s [Wegovy] promise now hinges on insurance coverage.”

In clinical trials, weekly injections of semaglutide — or Wegovy, as it’s been branded — helped people drop an average of 15% of their body weight. That’s an average of about 34 pounds over 16 months, before their weight plateaued, a far greater weight loss, obesity specialists say, than achieved with other drugs on the market. At least as important, Wegovy raised none of the alarm bells with the FDA or obesity doctors that it might trigger serious side effects of the sort some people experienced by taking fen-phen or other previous medical treatments for obesity.

But with a price tag for Wegovy of $1,000 to $1,500 a month, a big question remains: Will insurers cover its significant cost for the millions who might benefit? * * *

Insurance coverage, it turns out, is a giant question — not just with Wegovy but with obesity drugs in general. Some private insurers do include some prescription obesity drugs in the list of medicines they’ll cover; it’s too early to tell whether Wegovy will make those lists. Many doctors and patients are optimistic, because it is a higher dose of an existing diabetes medication called Ozempic, which insurers often cover.

A few select state Medicaid programs will cover medications that treat obesity in some circumstances. But, significantly, Medicare does not cover obesity drugs — and many private insurers typically follow Medicare’s lead.

Yet the demand for a good treatment is there, says Dr. Fatima Cody Stanford, a leading obesity researcher at Harvard. She was not involved in conducting the Wegovy clinical trial but closely followed it. “I’m excited about it,” she says, because of the dramatic weight loss.

The drug acts on the brain so people eat less and store less of what they eat. That helps address the excess weight as well as helping with related diseases of the liver or heart, for example.

  • The FEHBlog enjoys book recommendations and so he lapped up STAT’s list of “the 36 best books and podcasts on health and science to check out this summer. Among them, this one particularly caught the FEHBlog’s attention as he has enjoyed reading this author’s output and the topic is intriguing: “The Code Breaker: Jennifer Doudna, Gene Editing, and the Future of the Human Race” By Walter Issacson I recommend it because this captivating book provided clear and accessible explanations of the scientific discovery of CRISPR-Cas9 and its remarkable power as a gene editing tool, interwoven with the complex human stories of Jennifer Doudna and her relationships with the many other accomplished scientists who brought it all together.— Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases”

Holiday Weekend Update

Photo by Dane Deaner on Unsplash

Both Houses of Congress are on State / District work breaks this week.

From the COVID-19 front, the Wall Street Journal offers two important reports:

  • As the Delta variant of the coronavirus surges through the United Kingdom [U.K.], almost half of the country’s recent Covid-19 deaths are of people who have been vaccinated. But doctors and scientists aren’t sounding the alarm about the apparently high proportion of deaths among the vaccinated population. On the contrary, they say the figures so far offer reassurance that vaccines offer substantial protection against the variant, particularly after two doses. Delta, first identified in India, has since spread to at least 85 countries, including the U.S., where it is now estimated to be the most common variant.
  • Also here are the top line recommendations for what parents with unvaccinated children should know this summer: 1. Keep unvaccinated kids’ masks on indoors; 2. Look out for regional hotspots; 3. weigh travel plans carefully / stay closer to home; 4. consider higher precautions for higher risk children; 5. get your family vaccinated as soon as a family member becomes eligible; and check local recommendations before traveling.

From the cybersecurity front, the Journal updates us on the Kaseya ransomware situation:

The hackers were able to distribute ransomware by exploiting several vulnerabilities in the VSA software, a Kaseya spokeswoman said.

One of them, discovered by a Dutch security researcher, was in the process of being patched by Kaseya before the ransomware attack occurred, said Victor Gevers, chairman of the volunteer-run security group, the Dutch Institute for Vulnerability Disclosure.

“Kaseya understood the problem and they were rushing to produce a patch,” Mr. Gevers said. Mr. Gevers said the bug was due to a simple error in the company’s code.

About 50 of Kaseya’s customers were compromised and about 40 of those customers were sellers of IT services, known as managed service providers, Mr. Voccola said. By breaking into MSP’s, the hackers were able to expand their impact, performing what security experts call a supply-chain attack.

Security companies estimate that hundreds of organizations, all of them customers of those 40 or so service providers, have now been hit by the ransomware, making it one of the most widespread incidents to date. But almost all of them are small and medium-size organizations, cybersecurity experts said, with the impact often not immediately apparent to the wider public. * * *

The hackers behind the latest incident are known as the REvil ransomware group. They are asking for $70 million to unlock all the affected systems but victims of the group can also pay amounts varying between $25,000 and $5 million directly to unlock their systems even if nobody pays the $70 million.

In an eye-catching tidbit, Beckers Hospital Review reports that the staff at Fort Worth’s Andrews Women’s Hospital delivered 107 babies over a 91 hour period last week. A COVID baby boom?

Friday Stats and More

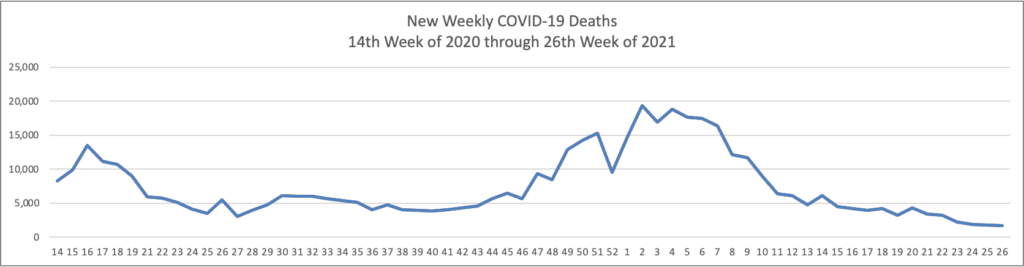
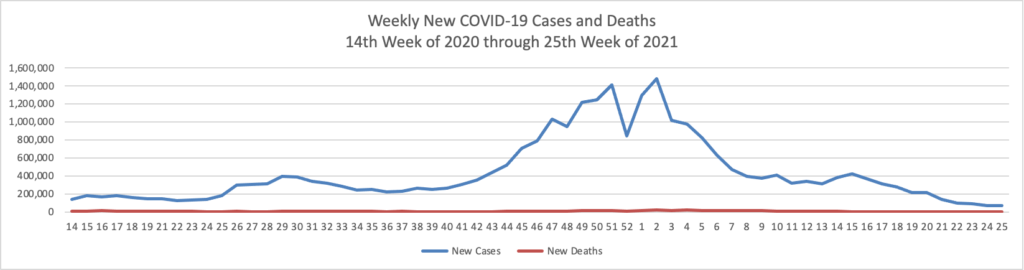
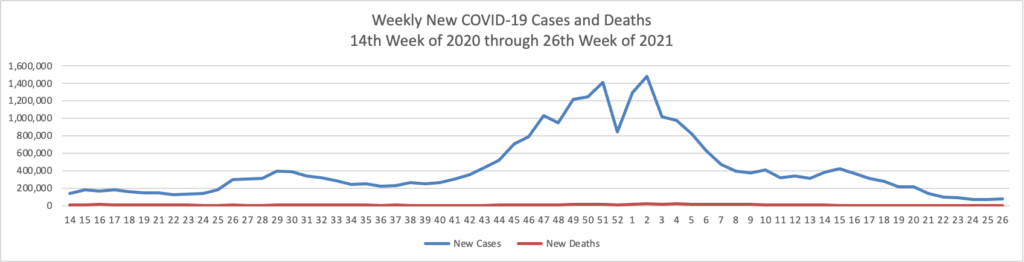
Based on the Centers for Disease Control’s (“CDC”) improved COVID-19 Data Tracker website, here is the FEHBlog’s chart of new weekly COVID-19 cases and deaths over the 14th week of 2020 through 26th week of this year (beginning April 2, 2020, and ending June 30, 2021; using Thursday as the first day of the week in order to facilitate this weekly update):

and here is the CDC’s latest overall weekly hospitalization rate chart for COVID-19:

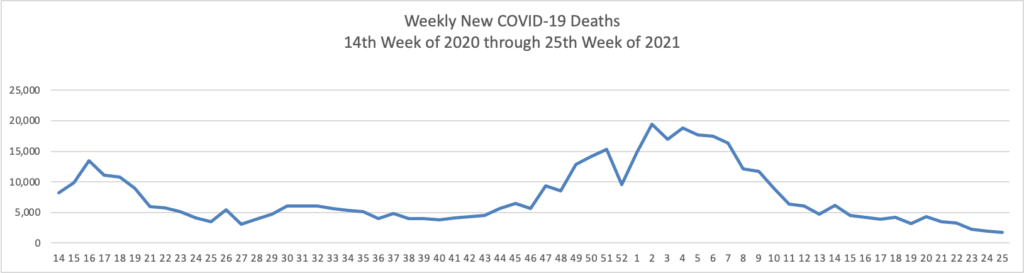
The FEHBlog has noticed that the new cases and deaths chart shows a flat line for new weekly deaths  because new cases significantly exceed new deaths. Accordingly here is a chart of new COVID-19 deaths over the period (April 2, 2020, through June 30, 2022):

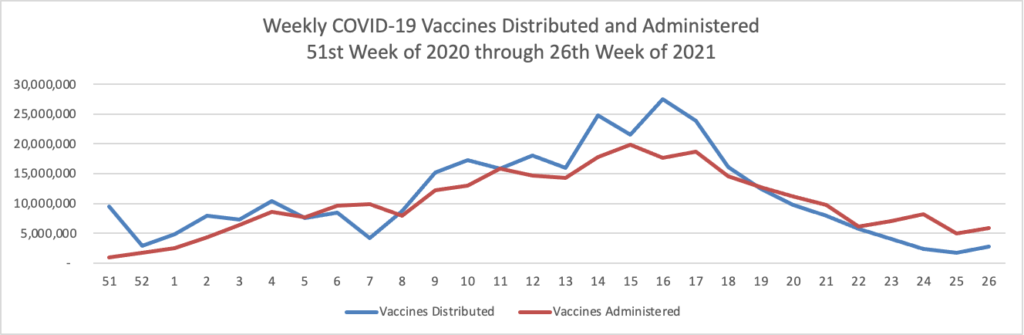
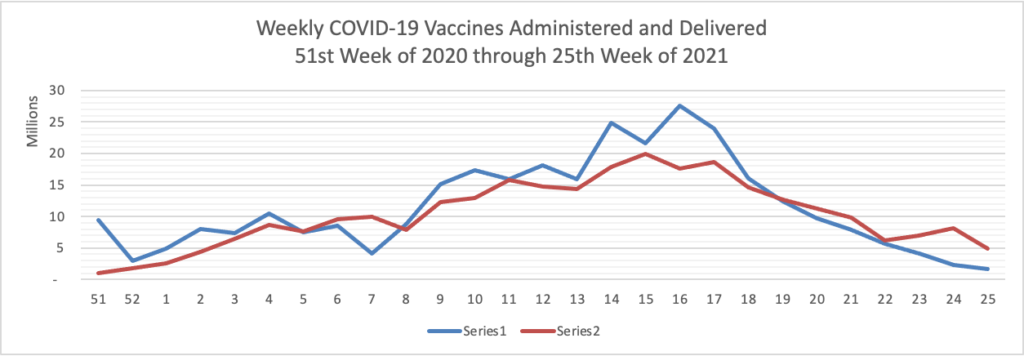
Finally here is a COVID-19 vaccinations chart over the period December 17, 2020, through June 30, 2022 which also uses Thursday as the first day of the week:

In its weekly COVID-19 update the CDC reminds us that

The emergence and spread of variants also have the potential to chip away at our nation’s progress to end this pandemic. On June 15, 2021, CDC announced classification of the SARS-CoV-2 variant B.1.617.2 (Delta) as a variant of concern because it spreads more easily. The spread of the more transmissible B.1.617.2 variant combined with the U.S. population that remains unvaccinated leaves many people at risk of infection. With B.1.617.2 now spreading across the country and infecting people worldwide, it’s more important than ever that all eligible people get vaccinated as soon as possible.

The COVID-19 vaccines authorized for use in the United States offer protection against all known variants, including the B.1.617.2 variant. Getting vaccinated will protect you and the people you love. COVID-19 vaccines are free and available for everyone ages 12 and up. They are nearly 100% effective against severe disease and death, meaning nearly every death due to COVID-19 is preventable. No matter your age, or your health history, until you’re fully vaccinated*—you are at risk of infection. By getting vaccinated and encouraging those around you to do the same, you can safely engage in activities you enjoyed prior to the COVID-19 pandemic. Get vaccinated, help others get vaccinated, and use prevention measures if not fully vaccinated so we can all celebrate our freedom from the virus.

Also from the COVID-19 front Becker’s Payer Issues reports that

The Vaccine Community Connectors program, which was launched by AHIP and the Blue Cross Blue Shield Association, has helped vaccinate more than 2 million people over 65 against COVID-19 in under 100 days, according to a July 1 news release.

More than 50 health insurers are now participating in the program, which was initiated to expand vaccination efforts of people in low-income communities.

“The most vulnerable people in our country have suffered disproportionately from the COVID-19 crisis, which is why we have been working side-by-side with industry partners to help millions of vulnerable Americans get vaccinated against the virus,” BCBSA CEO Kim Keck said in the statement.

Bravo! Health Payer Intelligence reports on how employers can best assist the nationwide vaccination campaign.

Seventy-three percent of workers whose employers encouraged them to receive the coronavirus vaccine had at least one vaccine shot. Additionally, 75 percent of those who received paid time off to get the vaccine have gotten at least one shot.

In contrast, only four in ten of those whose employers did not encourage employees to get vaccinated had received a coronavirus vaccine shot. Similarly, half of those whose employers did not provide paid time off to get the vaccine reported that they had received the coronavirus vaccine.

These distinctions remained true regardless of variations in race, age, ethnicity, income, and even regardless of whether the individual identified as Republican or Democrat.

In the more news category:

  • The U.S. Supreme Court today added two healthcare cases to its October 2021 docket. According to Law360, the Court “agreed to review whether the federal government lawfully cut billions of dollars from reimbursements for drugs bought through a discount program for hospitals in low-income areas, as well as a reimbursement calculation for hospitals that serve a high amount of low-income individuals.”
  • Benefits Pro reports that “Under pressure to rein in skyrocketing prescription drug costs, states are targeting companies that serve as conduits for drug manufacturers, health insurers and pharmacies. More than 100 separate bills regulating those companies, known as pharmacy benefit managers, have been introduced in 42 states this year, according to the National Academy for State Health Policy, which crafts model legislation on the topic. The flood of bills comes after a U.S. Supreme Court ruling late last year backed Arkansas’ right to enforce rules on the companies. At least 12 of the states have adopted new oversight laws. But it’s not yet clear how much money consumers will save immediately, if at all.” The source of the cost problem is not the PBMs who work with health plans to control costs. The PBMs vastly expanded prescription drug coverage for Americans. The sources of the cost problem are the manufacturers and wholesales. All these new state law simply adds more costs to the drug distribution process in the FEHBlog’s view.
  • Becker’s Payer Issues explains how the BCBSA chief innovation officer seeks to transform healthcare one step at a time. Good luck to her. The FEHBlog loves her title.

No Surprises Thursday

Photo by Josh Mills on Unsplash

The federal regulators, including the Office of Personnel Management, achieved their statutory deadline today for issuing the first round of No Surprises Act implementing rules. Here’s the regulators’ output, compliments of the Labor Department:

There is no doubt in the FEHBlog’s mind that the regulators did a fine job of making a silk purse out of sow’s ear / the poorly drafted statute. This rule will help carriers and providers meet the January 1, 2022, launch date. This law, if properly implemented, and signs are looking good now, will protect consumers from surprise medical bills, which was clearly Congress’s objective, but without creating an IT nightmare.

The regulators plan a second round of No Surprises Act rules for October 1, 2021. The second round will focus on the independent dispute resolution process.

From the COVID-19 front —

  • The New York Times reports that “The Johnson & Johnson coronavirus vaccine is effective against the highly contagious Delta variant, even eight months after inoculation, the company reported on Thursday — a finding that should reassure the 11 million Americans who have gotten the shot. The vaccine showed a small drop in potency against the variant, compared with its effectiveness against the original virus, the company said. But the vaccine was more effective against the Delta variant than the Beta variant, first identified in South Africa — the pattern also seen with mRNA vaccines.”
  • Medscape informs us that “The White House on Thursday announced it will send “strike teams” to 1000 counties where the COVID-19 Delta variant is spreading rapidly. The teams will be made up of health and logistics experts from several federal agencies and will conduct coronavirus testing, distribute medicines designed to fight the virus, and boost local and state efforts to increase vaccinations.”

In Thursday Miscellany —

  • GoodRx is tracking prescription drug manufacturer price changes which typically are made effecting January 1 and July 1.
  • The Centers for Medicare and Medicaid Services “is proposing actions that aim to close health equity gaps by providing Medicare patients battling End-Stage Renal Disease (ESRD) with greater access to care, through the ESRD Prospective Payment System (PPS) annual rulemaking. This proposed rule would update ESRD PPS payment rates, make changes to the ESRD Quality Incentive Program (QIP), and modify the ESRD Treatment Choices (ETC) Model.  The proposed changes to the ETC Model policies would aim to encourage dialysis providers to decrease disparities in rates of home dialysis and kidney transplants among ESRD patients with lower socioeconomic status, making the model the agency’s first CMS Innovation Center model to directly address health equity.”
  • The Aetna Foundation and U.S. News and World Report released their 2021 healthiest U.S. communities rankings this week.

2021 Healthiest Communities- Top 10

*See the full rankings here

Top 10 Counties

  1. Los Alamos County, New Mexico
  2. Douglas County, Colorado
  3. Falls Church, Virginia
  4. Loudoun County, Virginia
  5. Broomfield County, Colorado
  6. San Miguel County, Colorado
  7. Pitkin County, Colorado
  8. Howard County, Maryland
  9. Morgan County, Utah
  10. Routt County, Colorado

2021 Key Measures

Top 5 Communities for Health Outcomes

  1. San Juan County, Washington
  2. Marin County, California
  3. Carver County, Minnesota
  4. Stevens County, Minnesota
  5. Hunterdon County, New Jersey

Top 5 Communities for Access to Health Care

  1. Olmsted County, Minnesota
  2. Montour County, Pennsylvania
  3. Suffolk County, Massachusetts
  4. Johnson County, Iowa
  5. Perry County, Kentucky

Top 5 Communities for Mental Health

  1. Honolulu County, Hawaii
  2. Pitkin County, Colorado
  3. Fairfax County, Virginia
  4. Santa Clara County, California
  5. San Mateo, California

Midweek Update

Photo by Manasvita S on Unsplash

In news from our Nation’s capital

  • Yesterday the House Appropriations Committee approved for House floor consideration the Fiscal Year 2022 Financial Services and General Government appropriations bill which includes OPM and FEHB Program funding. The vote was 33-24. Govexec adds that the Committee action “endorses President Biden’s proposal to give civilian federal employees an average 2.7% pay raise in 2022, despite efforts by some Democrats to provide a bigger increase.”
  • Amy Howe informs us that tomorrow will be the last day of the U.S. Supreme Court’s October 2020 term and the two remaining decisions are politically significant.
  • The Society for Human Resource Management reports that ​”The Equal Employment Opportunity Commission (EEOC) has extended the deadline for filing the EEO-1 form from July 19 to Aug. 23. Businesses with 100 or more employees and some federal contractors with at least 50 employees must submit an annual EEO-1 form, which asks for information from the previous year about the number of employees who worked for the business, sorted by job category, race, ethnicity and gender. The EEOC did not collect such data in 2020 due to the coronavirus crisis. Covered employers now have until the new deadline to submit both their 2019 and 2020 data.”
  • The Office of Management and Budget’s Office of Information and Regulatory Affairs has completed its work on HHS’s first interim final rule on implementing the No Surprises Act. Next step will be the Federal Register’s public inspection list.

From the COVID-19 front

  • The Centers for Disease Control has improved its COVID-19 data tracker website. Check out this fascinating new chart on the value of the COVID-19 vaccines.
  • The Wall Street Journal reports that “People who became infected with Covid-19 after getting a messenger RNA vaccine [Pfizer or Moderna] carried less virus and had shorter cases than unvaccinated people who became infected, a study by government health researchers found. * * * “Even when people get vaccinated and did get infected, they were less likely to have an illness that causes a fever,” said Mark Thompson, an epidemiologist at the U.S. Centers for Disease Control and Prevention who helped lead the study.”
  • The American Hospital Association informs us that “The Moderna COVID-19 vaccine produces neutralizing antibody titers against the Delta variant, although fewer than against the ancestral strain of the virus, the company announced yesterday. * * * “These new data are encouraging and reinforce our belief that the Moderna COVID-19 Vaccine should remain protective against newly detected variants,” said CEO Stéphane Bancel.

From the Aduhelm front, STAT News tells us that
A majority of U.S. physicians disagree with the Food and Drug Administration’s approval of the Alzheimer’s drug from Biogen (BIIB) and believe the medicine should not be routinely used, according to a new survey from STAT and Medscape. Nearly two-thirds of the 200 primary care physicians and neurologists polled find the trial data unclear when it comes to benefits and risks of the drug. Consequently, only a small minority of these doctors think the medicine should be given to patients with early-onset Alzheimer’s.

The controversial new Alzheimer’s drug would only be cost effective if priced between $3,000 and $8,400, an 85% to 95% discount off the $56,000 list price, due to “insufficient” evidence the drug benefits patients, STAT says, citing a revised analysis. The assessment by the Institute for Clinical and Economic Review is very similar to an evaluation issued a month ago, before the FDA approved the medicine and issued a broad label. But Biogen has pledged to promote the drug only to a more specific patient population and the FDA is requiring fewer costly MRI scans to monitor patient safety.

With regard to the physician survey and with all due respect to that fine profession, the FEHBlog expects that the “If you build it they will come” principle could apply to Aduhelm.

In other healthcare news

  • Barron’s reports that “The nation’s largest retailer is now selling the first private-label insulin at prices more than 50% lower than brand names of the diabetes drug, which can cost thousands of dollars a year. Walmart pharmacies began filling prescriptions this week for the discount chain’s ReliOn NovoLog brand of insulin in vials and injector pens. The drug, made by major supplier Novo Nordisk (NVO), will be available by mid-July at the company’s Sam’s Club wholesale stores. “We know many people with diabetes struggle to manage the financial burden of this condition, and we are focused on helping by providing affordable solutions,” Cheryl Pegus, executive vice president of Walmart Health & Wellness, announced Tuesday.” 
  • Medscape informs us that “Families with private health insurance pay around $3,000 for newborn delivery and hospitalization, while adding neonatal intensive care can push the bill closer to $5,000, based on a retrospective look at almost 400,000 episodes. The findings suggest that privately insured families need prenatal financial counseling, as well as screening for financial hardship after delivery, reported lead author Kao-Ping Chua, MD, PhD, assistant professor and health policy researcher in the department of pediatrics and the Susan B. Meister Child Health Evaluation and Research Center at the University of Michigan, Ann Arbor, and colleagues. “Concern is growing regarding the high and rising financial burden of childbirth for privately insured families,” the investigators wrote in Pediatrics.”  Health plans may want to take a gander at their own members out of pocket spending on maternity care.
  • Employee Benefit News inquires whether a “subscription model can fix primary care.” The subscription model is offered by direct primary care companies like One Medical. According to the EBN article,

The appeal of these companies has grown as employers increasingly seek to address a shortage of high-quality primary care and reduce spending on the health of their workforce, said Ellen Kelsay, CEO and president of the Business Group on Health, which represents large employers.

Studies show a strong correlation between access to primary care and lower spending on expensive medical services such as ER visits, surgeries and hospital admissions. Yet in the United States, primary care accounts for only around 5% to 7% of total health spending, compared with 14% in the 36 member nations of the Organization for Economic Cooperation and Development.

The big bet of One Medical and companies like it is that greater spending on primary care will fatten their bottom lines while reducing overall health costs for their clients. [One Medical works with health plans as well as self-funded employers and patients.]

Tuesday’s Tidbits

Photo by Patrick Fore on Unsplash

In today’s Morning Rounds email, the American Medical Association informs us that

The New York Times (6/28, Mandavilli) reports a new study published in Nature has found the COVID-19 vaccines from Pfizer-BioNTech and Moderna “set off a persistent immune reaction in the body that may protect against the coronavirus for years, scientists reported on Monday.” Researchers gathered samples from the lymph nodes of 14 recruits at five different points following the first dose, finding “the number of memory cells that recognized the coronavirus had not declined” 15 weeks later. The Times adds, “The results suggest that a vast majority of vaccinated people will be protected over the long term.”

In a separate article, the New York Times (6/28, Mandavilli, Zimmer, Robbins) says the study adds to other research suggesting that “widely used vaccines will continue to protect people against the coronavirus for long periods, possibly for years, and can be adapted to fortify the immune system still further if needed.”

The Federal Times reports that GEHA, the second largest FEHB plan carrier, has launched a COVID-19 vaccination reward program for its members. Here is a link to GEHA’s website on this program.

As of today just about two thirds of Americans over age 18 have had at least one dose of a COVID-19 vaccination. Most importantly, approaching 90% of Americans over age 65, the cadre that suffered the most COVID-19 fatalities, has received at least one dose of the COVID-19 vaccine and 78% of that cadre are fully vaccinated. However, Bloomberg warns that

The gap between the most vaccinated and least vaccinated places in the U.S. has exploded in the past three months, and continues to widen despite efforts to convince more Americans to get a Covid shot. * * * In the least vaccinated group of counties, many of which are in the South and Central regions of the U.S., less than half as many people have gotten at least one Covid vaccine dose as in the most vaccinated counties in the cities and on the coasts. Those less vaccinated places are not catching up, either. The gap between more- and less-vaccinated counties is expanding, and the trailing counties are far below levels needed to halt future waves of infection. 

As the FEHBlog has pointed out previously, such herd immunity is built on both natural immunity and vaccination-created immunity. The FEHBlog encourages COVID-19 vaccination which has been miraculous. Nevertheless you cannot predict Delta variant devastation in certain areas of our country without considering natural immunity and the fact that most of elderly cadre is vaccinated. The FEHBlog also has confidence in the federal, state and county authorities as well as the Nation’s physicians to complete the vaccination campaign.

And now for Tuesday’s tidbits

  • The FEHBlog nearly fell off his chair when he read in Healthcare Dive that Nearly 70% of U.S. physicians are now employed by a hospital or a corporate entity, according to the latest report by Avalere for the Physicians Advocacy Institute, a coalition of state doctors’ groups. This is the first time the report included ownership by corporate entities outside of just hospitals. Hospitals and corporate entities, which include insurers or private equity groups, own nearly half of the physician practices in this country, according to the report released Tuesday that examines the two-year period from 2019 through 2020.  This longtime trend [really since the Affordable Care Act became law in 2010] was exacerbated during the COVID-19 pandemic, according to the report, which shows 48,400 physicians left private practice during the study period across all regions of the country.” The FEHBlog does not see this course reversing itself.
  • Buck consultants reminds FEHB plan carriers that the PCORI fee is due on August 2 this year because July 31 falls on a Saturday.
  • Medscape reports that “In the U.S. House [of Representatives], 20 Democrats and 10 Republicans have signed on as co-sponsors to the Protecting Seniors Through Immunization Act of 2021 (HR 1978), introduced in March by Rep. Ann Kuster (D-NH). The companion Senate measure (S 912) has the backing of two Democrats and two Republicans. This legislation would end copays in Medicare Part D plans for vaccines recommended for adults by the CDC’s Advisory Committee on Immunization Practices.” The FEHBlog, who is on Medicare, got hit for $400 in copayments to obtain two doses of the new ACIP recommended Shingles vaccine last year. Why it is taking over a decade for Medicare to align with the ACA on this point is beyond the FEHBlog’s understanding.
  • AHRQ’s Director Dr. David Meyers offers his perspective on getting telehealth properly integrated into our health care system.
  • The showstopper of this week will be the first interim final rule on implementation of the No Surprises Act which has a statutory deadline of Thursday July 1. The rule is expected to principally pertain to calculating the initial payments in the NSA scenarios. Hopefully the rule will provide more guidance than that. The rule has been pending approval from the Office of Management and Budget’s Office of Information and Regulatory Affairs since June 8. Since then OIRA has sponsored seven listening sessions with interested organizations. The last such listening session will be held tomorrow at 1 pm ET. Once the listening session is completed, a list of attendees and the meeting materials are posted on OIRA’s online calendar.

Monday Roundup

Photo by Sven Read on Unsplash

Bloomberg has released its latest COVID-19 resilience ranking.

Almost a year and a half into the pandemic, the best and worst places to be in the Covid-19 era are increasingly defined by one thing: normalization.

The biggest vaccination drive in history is enabling parts of the globe to abolish mask mandates, relax restrictions and dismantle border curbs, making the magnitude of reopening key to quality of life. Taming cases and deaths was once paramount, along with ensuring a robust health-care system. Now, the ability to essentially turn back the clock and return to pre-pandemic times is taking on an even greater significance.

Central to that is an economy’s openness to the world, and that’s why we’ve introduced a new element—Reopening Progress—to Bloomberg’s Covid Resilience Ranking. Two new metrics capture the ease of moving in and out of a place and how much air travel has recovered, alongside our 10 other measures tracking mortality rates to infection counts, freedom of movement to economic growth.

This pivot has ushered in dramatic changes to the ranks. The U.S. is now No. 1, with its fast and expansive vaccine rollout, dominated by the highly effective Messenger RNA shots, stemming what was once the world’s worst outbreak.

The U.S. Supreme Court today according to Fierce Healthcare

declined to hear an appeal of a lower court decision upholding the Department of Health and Human Services’ (HHS’) site-neutral payments policy.

The appeal was requested by the American Hospital Association (AHA) in February as part of a multiyear legal battle challenging HHS’ authority to bring Medicare payments to off-campus clinics in line with independent physician practices. The AHA’s bid was supported by a long list of other provider industry stakeholders.

By taking a pass on the case, the top court has now paved the way for HHS to move forward with the 2019 Outpatient Prospective Payment System rule—a policy the agency has said would have saved the Centers for Medicare & Medicaid Services roughly $800 million in payments to outpatient departments during 2020. * * *

HHS’ rule aims to remove payment disparities where hospital-affiliated clinics receive more Medicare reimbursement than physicians’ offices providing the same services. Researchers have suggested over the years that these disparities have played a part in provider consolidation.

Also today the Department of Health and Human Services released a third notice of Affordable Care Act Benefit and Payment Parameters as a proposed rule. Fierce Healthcare informs us that the proposed rule would set the ACA’s open season at an expanded November 1 through January 15 and also would allow exchanges to offer special enrollment periods for low income customers who may benefit from the American Rescue Plan’s expanded premium credits. Health Payer Intelligence discusses two impacts from the current ongoing special ACA open enrollment period which runs until August 15.

In other round up items

  • The ICD-10 Monitor tells us that the Centers for Disease Control released new ICD-10-CM codes for federal fiscal year 2022 which include 19 new social determinants of health codes in the “Z” chapter. Many of these new “Z” codes are attributable to the Gravity Project which is an HL7 FHIR accelerator organization.
  • The Wall Street Journal discusses what doctors want their patients to know about the new Alzheimer’s disease drug Aduhelm. For example, “The treatment would work over years, not weeks or months. Dr. [Paul] Aisen estimates that patients with mild cognitive impairment, which is often a precursor to dementia, might get an extra year or two before they start losing their ability to function independently.”
  • Fierce Healthcare reports that

Future demand for healthcare services will be relatively flat to declining, with little to no effect from the COVID-19 pandemic, according to a new forecast report.

At the same time, hospitals and health systems are facing increasing competition from consumer businesses such as Amazon and Walmart, retail behemoths that are rapidly expanding the supply of healthcare services.

The implications of softening demand and increasing supply suggest that pricing trends are ultimately unsustainable for healthcare providers, according to a new report from health system analytics company Trilliant Health.

The company’s analysis, based on 70 billion medical claims across 309 million patient visits, contradicts the commonly held belief that the demand for healthcare services nationwide is rising, according to Sanjula Jain, Ph.D., senior vice president of market strategy and chief research officer at Trilliant Health.

Time will tell.

Friday Stats and More

Based on the Centers for Disease Control’s COVID-19 Data Tracker website, here is the FEHBlog’s chart of new weekly COVID-19 cases and deaths over the 14th week of 2020 through 25th week of this year (beginning April 2, 2020, and ending June 23, 2021; using Thursday as the first day of the week in order to facilitate this weekly update):

According to the Centers for Disease Control (“CDC”),

The current 7-day moving average of daily new cases (11,343) decreased 4.4% compared with the previous 7-day moving average (11,867). Compared with the highest peak on January 10, 2021 (252,166), the current 7-day average decreased 95.5%. A total of 33,409,895 COVID-19 cases have been reported as of June 23.

Here is the CDC’s latest overall weekly hospitalization rate chart for COVID-19 which also has been steadily decreasing:

The FEHBlog has noticed that the new cases and deaths chart shows a flat line for new weekly deaths  because new cases significantly exceed new deaths. Accordingly here is a chart of new COVID-19 deaths over the period (April 2, 2020, through June 23, 2021):

Finally here is a COVID-19 vaccinations chart over the period December 17, 2020, through June 23, 2021, which also uses Thursday as the first day of the week:

As of today, according to the Centers for Disease Control, over 150 million Americans are fully vaccinated. The vaccination campaign has lead to the low levels of new cases and deaths in our country. The Associated Press observes:

Nearly all COVID-19 deaths in the U.S. now are in people who weren’t vaccinated, a staggering demonstration of how effective the shots have been and an indication that deaths per day — now down to under 300 — could be practically zero if everyone eligible got the vaccine.

An Associated Press analysis of available government data from May shows that “breakthrough” infections in fully vaccinated people accounted for fewer than 1,200 of more than 853,000 COVID-19 hospitalizations. That’s about 0.1%.

And only about 150 of the more than 18,000 COVID-19 deaths in May were in fully vaccinated people. That translates to about 0.8%, or five deaths per day on average.

The CDC also reminds us that

Currently, several variants are found around the world, including in the United States. On June 15, 2021, the B.1.617.2 (Delta)* variant was classified as a VOC because it spreads from person to person more easily than other variants and may cause more severe disease. B.1.617.2 has been reported in 77 countries and in the United Kingdom has become the main variant in COVID-19 cases. In the United States, the proportion** of B.1.617.2 for the 2-week period ending June 19, 2021, is predicted to increase to 20.6% nationally and be higher in regions 2, 6, 7, 8, and 9.

The more a virus circulates in a population, the more opportunities it has to transform itself and can reduce the effectiveness of our vaccines. Recent studies have shown that the vaccines available in the United States are effective against variants currently circulating, including B.1.617.2. Vaccines interrupt the ability of the virus that causes COVID-19 to move between people and mutate, so it is important for everyone to get vaccinated as soon as they’re eligible. If you have questions or concerns about vaccines, please contact your healthcare professional, state or local health department, or local pharmacist or visit the CDC website. To find a place in your community to get a vaccine, visit Vaccines.gov or your local public health department website.

In the More department

  • The American Managed Care Journal reports that AHIP hosted a small group of U.S. Senators at a recent conference where the Senators offered their thoughts on future federal healthcare legislation.
  • Tammy Flanagan in Govexec discusses NARFE’s legislative conference on pending legislation in Congress affecting federal employees, annuitants and their benefit programs, including the Postal Reform Act.
  • Healthcare Dive informs us that “The Biden administration’s top health policy official on Thursday [June 24] reiterated his support for expanded telehealth access after the COVID-19 national emergency expires, as Congress considers a slate of bills that would permanently nix regulatory barriers to virtual care. “We are absolutely supportive of efforts to give us the authority to utilize telehealth in greater ways,” HHS Secretary Xavier Becerra said at a virtual event on digital health hosted by The Washington Post. Becerra also stressed that, though affordable telehealth should be available to all, HHS would be doubling down in making sure there’s accountability for quality of care. “We’re going to be doing a lot of bird-dogging, a lot of oversight,” he said.”
  • Fierce Healthcare reports on the winners of the IBM XPrize competition to create artificial intelligence tools to tackle global problems. For example, “An Israeli startup that uses artificial intelligence and other tech tools to wipe out malaria took the top prize in IBM Watson’s AI competition, nabbing $3 million to expand its operations. ZzappMalaria, a subsidiary of Sight Diagnostics, developed an AI-powered mobile app and dashboard to tackle malaria on the eradication level, specifically in developing countries.” Very 21st Century.

Welcome Director Ahuja

OPM Headquarters a/k/a the Theodore Roosevelt Building

OPM’s new Director Kiran Ahuja was sworn in today. Here is a link to the OPM press release on the festivities.

Health Payer Intelligence informs us that “The Alliance of Community Health Plans (ACHP) has proposed a number of recommendations to improve the Federal Employees Health Benefits (FEHB) program’s plan comparison tool in order to boost quality and enrollment, according to a recent issue brief.” ACHP’s action is timely because OPM has been focusing attention on the plan comparison tool in consultation with interested carriers and presumably other stakeholders.

According to a Committee press release, “The House Appropriations Subcommittee on Financial Services and General Government today approved by voice vote its fiscal year 2022 bill. [This is the bill that funds OPM and the FEHB.] For fiscal year 2022, the draft bill includes $29.1 billion in funding, an increase of $4.8 billion over 2021.” 

Sen. Chuck Grassley (R Iowa) announced

Sen. Chuck Grassley (R-Iowa) today joined Senate Majority Whip Dick Durbin (D-Ill.) Sen. Angus King (I-Maine) to introduce the Drug-price Transparency for Competition (DTC) Act, a bill that would require price disclosures on advertisements for prescription drugs, in order to empower patients and reduce spending on medications. Last week, the Government Accountability Office (GAO) released a report – requested by Durbin and Grassley – which found direct-to-consumer (DTC) advertisements of prescription drugs contribute to an enormous amount of Medicare costs. Specifically, the DTC Act would require DTC advertisements for prescription drugs and biological products to include a disclosure of the list price, so that patients can make informed choices when inundated with drug commercials. 

Speaking of drug prices, let’s take a look at recent news on the new Alzheimer’s Disease drug, Aduhelm.

  • Yesterday, Biogen issued a bulleted defense of its pricing, which is $56,000 annually per patient. STAT News points out “For families and physicians grappling with the historic approval this month of the controversial Alzheimer’s drug Aduhelm, there’s no shortage of unanswered questions. But a critical one has largely been overlooked: Once patients start taking the medication, how will they know when it’s time to stop? “We don’t have any guidance on how long to give this medication to someone who doesn’t experience adverse events,” said William Mantyh, a behavioral neurologist at M Health Fairview University of Minnesota Medical Center. “With a drug like aducanumab where the upfront demonstrated efficacy is up in the air, it really makes it hard for a clinician to figure out when to stop the drug based on a patient’s clinical symptoms.”
  • Axios interviewed AHIP CEO Matt Eyles on Aduhelm pricing. In response to an Axios question on acceptable pricing, Mr. Eyles responded that “The best information we have is what [the Institute for Clinical and Economic Review] puts out.” ICER stated on June 7 that “At the ICER public meeting on aducanumab on July 15, 2021, we will tackle important questions [about Aduhem] with all stakeholders at the table. We will also address the question of fair pricing for a drug that now seems likely to become one of the top selling drugs in the history of the United States. ICER’s preliminary draft report calculated a fair annual price to lie between $2,500-$8,300. Even in our most optimistic cost-effectiveness scenario — which ignores the contradictions within the two pivotal trials and presumes that only the positive trial captures the true benefits of treatment — aducanumab’s health gains would support an annual price between $11,100-$23,100. The list price of $56,000 per year announced today by the drug maker far exceeds even this optimistic scenario. Our report notes that only a hypothetical drug that halts dementia entirely would merit this pricing level. The evidence on aducanumab suggests that, at best, the drug is not nearly this effective. Nonetheless, even at the lower range of the estimated number of eligible patients, at this price the drug maker would stand to receive well in excess of $50 billion per year even while waiting for evidence to confirm that patients receive actual benefits from treatment.
  • The Wall Street Journal reports that “Eli Lilly & Co. plans to submit its Alzheimer’s drug for market clearance under an expedited review this year, in a sign that regulators are encouraging development of treatments for the disease after a recent approval. Lilly said Thursday that the U.S. Food and Drug Administration had designated the company’s experimental Alzheimer’s drug, called donanemab, for the agency’s accelerated approval process. The FDA decision comes after the agency cleared Biogen Inc.’s Aduhelm, the first Alzheimer’s therapy to receive approval in nearly two decades but one that has drawn criticism from doctors and researchers skeptical the drug works. * * * Donanemab performed better in a trial than Biogen’s drug did in its trials, and health insurers and patients would probably prefer it over Aduhelm, J.P. Morgan analyst Chris Schott said in a note to investors.“Donanemab’s approval would be a major blow to Aduhelm’s commercial prospects,” Brian Skorney, a Robert W. Baird & Co. analyst, said in a research note. “We think it would make zero sense for FDA to approve Aduhelm, but not donanemab.” Ah, competition.

In other drug pricing news, Fierce Healthcare tells us that

Cigna is launching a new program that aims to incentivize eligible members to switch to biosimilar drugs.

Under the new Shared Savings Program, members will be offered a one-time $500 debit card for healthcare services or medications if they make the decision to switch to a biosimilar, according to an announcement provided first to Fierce Healthcare.

The program will be made available first to [approximately 7,000] eligible patients taking Remicade, a brand-name biologic that treats a number of inflammatory conditions such as Crohn’s disease and psoriasis. Remicade infusion costs can vary, but Cigna claims data suggest the average regimen costs $30,000 per year, with expenses growing depending on the site of administration.

Two biosimilars for the drug, Avsola and Inflectra, will be moved to the insurer’s preferred tier in July. Eligible customers and their providers will be notified by Cigna about their eligibility to participate in the Shared Savings Program in the coming weeks, the insurer said.

In COVID-19 news —

  • Fierce Biotech reports that “The FDA green-lit its first antibody test that doesn’t use blood samples to check for evidence of a COVID-19 infection and instead relies on simple, painless mouth swabs. Developed by Diabetomics, the rapid, lateral-flow diagnostic received an agency emergency authorization allowing it to be used at the point of care for adults and children. Designed to deliver a result within 15 minutes, the CovAb test also does not require any additional hardware or instruments. When administered at least 15 days after the onset of symptoms, when the body’s antibody response reaches higher levels, the test demonstrated a false-negative rate of less than 3% and a false-positive rate of nearly 1%, according to the company.” 
  • The New York Times reports that the Baltimore Maryland factory that had been producing the single dose Johnson & Johnson COVID-19 vaccine remains shuttered which Congress investigates its owner Emergent Biosolutions.
  • The NIH Director’s blog informs us about new NIH research on how Immunity generated from COVID-19 vaccines differs from an Infection. “The good news so far is that, unlike the situation for the common cold, we have now developed multiple COVID-19 vaccines. The evidence continues to suggest that acquired immunity from vaccines still offers substantial protection against the new variants now circulating around the globe. The hope is that acquired immunity from the vaccines will indeed produce long-lasting protection against SARS-CoV-2 and bring an end to the pandemic. These new findings point encouragingly in that direction. They also serve as an important reminder to roll up your sleeve for the vaccine if you haven’t already done so, whether or not you’ve had COVID-19. Our best hope of winning this contest with the virus is to get as many people immunized now as possible. That will save lives, and reduce the likelihood of even more variants appearing that might evade protection from the current vaccines.” Amen to that.

In a bit of Thursday miscellany

  • Patient Engagement reports that “Optum is bringing healthcare right into Utah’s backyard, rolling out a new Optum Mobile Health Clinic to improve care access for individuals in Optum Care Network Utah. The mobile health clinic, a 45-foot-long vehicle with two private exam rooms, a waiting room, and an imaging lab, is set to address the leading care access barriers experienced by Utahns.” Well done.
  • A friend of the FEHBlog called his attention to the NIH report on an engaging study suggesting scientists may need to rethink which genes control aging.

Midweek Update

Photo by Manasvita S on Unsplash

In anticipation of tomorrow morning’s markup session, the House Appropriations Committee today released the draft Fiscal Year 2022 financial services and general government appropriations bill. Of note,

  • Office of Personnel Management (OPM) – The bill includes $372 million, an increase of $42 million above the FY 2021 enacted level, for OPM to manage and provide guidance on Federal human resources and administer Federal retirement and health benefit programs.
  • [The bill] eliminates provisions preventing the FEHBP from covering abortion services [subject to limited exceptions, e.g. life of the mother is endangered by continuing the pregnancy].

Govexec.com adds that “the bill makes no mention of a pay raise for federal employees, effectively endorsing [President] Biden’s plan to give feds an average 2.7% pay raise next year. It remains unclear how the White House would divvy up the 2.7% between an across-the-board increase to basic pay and an average increase in locality pay, although traditionally 0.5% has been reserved for locality pay increases.

From the COVID-19 front, the American Hospital Association informs us

The AHA today joined the Department of Health and Human Services, Centers for Disease Control and Prevention, and other national health care and public health organizations in encouraging COVID-19 vaccination for everyone age 12 and older who is eligible. “Today, the CDC Advisory Committee on Immunization Practices (ACIP) met to discuss the latest data on reports of mild cases of inflammation of the heart muscle and surrounding tissue called myocarditis and pericarditis following COVID-19 vaccination among younger people,” the statement notes. “The facts are clear: this is an extremely rare side effect, and only an exceedingly small number of people will experience it after vaccination. Importantly, for the young people who do, most cases are mild, and individuals recover often on their own or with minimal treatment. In addition, we know that myocarditis and pericarditis are much more common if you get COVID-19, and the risks to the heart from COVID-19 infection can be more severe.” 

Separately, the Food and Drug Administration today told ACIP that it was moving quickly to adjust the language on its emergency use authorization fact sheets for the Pfizer and Moderna COVID-19 vaccines to note a likely association in rare cases of myocarditis and pericarditis in vaccine recipients.

Bloomberg reports in this regard that

CDC Director Rochelle Walensky said Wednesday that mRNA vaccines have been successful in preventing severe illness and death among young people. For every million second doses of an mRNA vaccine administered to those 18-to-24-year-olds, the CDC projects 26,000 cases of Covid and 1,657 hospitalizations are prevented, while only 49 to 61 cases of myocarditis may develop. Speaking at the Milken Institute Future of Health Summit, Walensky added that the data presented at the advisory committee meeting still “overwhelmingly demonstrate that the benefits of vaccination far outweigh the risks.”

The Society for Human Resource Management offers advice on confronting COVID-19 vaccination misinformation in the workplace.

From the prescription drug front, Fierce Healthcare reports that employer groups are asking Congress to look into Biogen’s pricing of its new Alzheimer’s drug at $56,000 per course of treatment and the CVS Health continues to remove hyperinflationary drugs from its formularies in order to control drug spending.

Posaconazole, an antifungal medication, is priced at $4,500 for a 30-day supply—while an alternative, fluconazole, costs less than $14. This is an example of a growing trend: medications, including many generics, with “hyperinflated” prices, experts at CVS Caremark say. The pharmacy benefit manager giant culled 72 such drugs from its formulary in 2020 alone, leading to savings of $1.2 billion compared to 2018.

From the price transparency world, RevCycle Intelligence tells us that “The majority of the top 100 hospitals by gross revenue are using a price estimator tool to comply with a landmark hospital price transparency rule from HHS, according to a recent study.”

Finally, CIGNA has added a telemental service called Brightside to its behavioral health network. According to the provider’s press release,

Brightside, a mental health telemedicine platform that offers access to high-quality anxiety and depression care from anywhere, today announced that it has joined the national behavioral health network for Cigna Corporation, a global health service company. Cigna’s 14 million behavioral health customers can now access Brightside’s evidence-based and data-driven approach to treating anxiety and depression through their commercial health care plans.” * * * “The pandemic has shined a light on the need for broader, more convenient access to mental health care. Cigna is committed to providing our customers with the behavioral health care they need, when and where they need it – and that is what Brightside will help us offer,” said Dr. Doug Nemecek, Cigna’s chief medical officer for behavioral health. “By increasing access through virtual care, customers can talk to a psychiatrist or therapist from the comfort and privacy of their homes. This is another demonstration of our commitment to provide timely and convenient access to depression and anxiety care for Cigna members.

The FEHBlog appreciates such services because in contrast to in person care where the mental health providers are typically out of network, telemental providers in a spoke and hub arrangement like this one are always in-network, thereby creating savings for the plan and the member.