Tuesday’s Tidbits

Tuesday’s Tidbits

From the Open Season advice front, here are recent articles from FedSmith and Govexec .

From Capitol Hill, FedWeek reports that last Wednesday Nov. 3

The Senate Homeland Security and Governmental Affairs Committee has approved:

HR-2662, to give agency IGs authority to subpoena former federal employees; require an administration to provide a “substantive rationale, including detailed and case-specific reasons” prior to removing an IG; limit the use of administrative leave for IGs, including during the 30 days following the removal announcement; require acting IGs to be selected from among senior-level employees within the watchdog community; and require regular training to IG employees on their whistleblower rights.

The House already has passed the HR 2662. The Senate Committee amended the House bill before voting to sending the “favorable” substitute bill to the Senate floor for a vote.

From the Delta variant front Medscape informs us that

Pfizer and its European partner BioNTech have asked the US Food and Drug Administration (FDA) to expand emergency authorization of its COVID vaccine to allow everybody 18 and older to get a booster dose.

If it goes through, the broader use of Pfizer boosters would be a step toward President Joe Biden’s goal of boosters for all adults. He announced the goal last August but backed off to let the regulatory process by the FDA and the Centers for Disease Control and Prevention (CDC) play out.

Pfizer is submitting a study of booster effects on 10,000 people to make its case, according to a company news release.

This would be Pfizer’s second bite at the FDA apple for this approach to its booster.

Govexec informs us from the Delta variant vaccine mandate front that

VA Secretary Denis McDonough spoke at the National Press Club in Washington, D.C. on Tuesday afternoon, which came after the October 8 deadline for health care employees to get vaccinated but before the November 22 deadline for the rest of the federal workforce. 

“We’re still getting all of our data together,” he said. As of this morning, about 91% of the health care professionals at VA “have uploaded their data,” which could be proof of vaccination or requests for one of the exemptions. This is up from about 70% about two and a half weeks ago. 

“We’re not going to question the legitimacy of anyone’s individual declaration of a religious exception,” McDonough said. However, “we may find ourselves in a situation where, for example, in an oncology department or in a spinal cord injury facility or in an intensive care unit…or community living center[s], we may have so many people who have claimed a religious exemption that we can’t safely provide care to our veterans in those vulnerable situations, in which case we reserve the right to deny religious exemptions.” 

Fedweek cautions that “Both supporters and opponents of the Coronavirus vaccine mandate expect it to increase turnover among federal employees, although it is hard to say how large that increase will be and how much of it will be involuntary versus voluntary.”

From the No Surprises Act (NSA) front, the FEHBlog noticed that the Centers for Medicare and Medicaid Services has created a public NSA website. Posted on the site is an October 25, 2021, CMS letter announcing required federal government website and contact information to be included in the consumer notice about the NSA and other NSA related documents.

Website: https://www.cms.gov/nosurprises/consumers. Note, consumer and provider functionality for complaints inquiry and triage will not be operational until January 2022.

Phone number for information and complaints: 1-800-985-3059.

We ask regulated entities not to include the above phone number in any plan documents for any plan or policy years that begin before January 1, 2022.

In other healthcare news

Per Fierce Healthcare, here are the 10 most cost-efficient hospitals in the U.S., according to the Lown Institute: 

  1. Pinnacle Hospital (Crown Point, Indiana)
  2. Saint Mary’s Regional Medical Center (Reno, Nevada)
  3. Mercy Medical Center Dubuque (Dubuque, Iowa)
  4. Encino Hospital Medical Center (Encino, California)
  5. Park Ridge Health (Hendersonville, North Carolina)
  6. Oroville Hospital (Oroville, California)
  7. Saint Michael’s Medical Center (Newark, New Jersey)
  8. UnityPoint Health – Meriter (Madison, Wisconsin)
  9. East Liverpool City Hospital (East Liverpool, Ohio)
  10. Maple Grove Hospital (Maple Grove, Minnesota)

“Overall, if all hospitals performed as well as the most cost-efficient hospitals, Medicare would save $8 billion each year.”

Healthcare Dive informs us that

Nonprofit health giant Kaiser Permanente’s operating margin continued to shrink in the third quarter as expenses grew faster than revenue, spurred by labor unrest and surging COVID-19 patients, the Oakland, California-based integrated health system said.

Kaiser reported $38 million in operating income in the quarter, on $23.2 billion in revenue. That’s a 0.2% operating margin — exceedingly low compared to a margin of 2.1% same time last year. 

The 39-hospital system’s expenses in the third quarter grew 7.5% year over year to $23.1 billion, while revenue only increased 5.5%. Kaiser said the expense growth was due to higher costs from COVID-19 patients and workforce requirements, as — like other hospital operators — Kaiser has had to pay more for travel nurses and other contract labor to meet rising patient levels during the pandemic.

Monday Roundup

Photo by Sven Read on Unsplash

From the FEHB Open Season front, consultant Tammy Flanagan reports on the new trend of FEHB plans to offer Medicare Part B premium reimbursement contingent upon joining a related Medicare Advantage plan.

From the Delta variant front, the American Hospital Association informs us that

The Food and Drug Administration Friday authorized another over-the-counter COVID-19 diagnostic test for emergency use. The iHealth COVID-19 Antigen Rapid Test delivers results in 15 minutes. The company anticipates producing 100 million tests per month, with capacity increasing to 200 million per month in early 2022, FDA said.

STAT News offers an interesting snapshot of the now diminishing Delta variant surge.

Chart comparing hospitalizations by vaccine status

The chart truly speaks for itself.

In the maternal health field, the Health and Human Services Department announced that “200+ hospitals that are participating in the HHS Perinatal Improvement Collaborative, a contract with Premier, Inc. This new network is focused on improving maternal and infant health outcomes by reducing disparities. Comprised of hospitals from all 50 states, the collaborative is the first to evaluate how pregnancy affects overall population health by linking inpatient data of newborns to their mothers.” A list of the participating hospitals may be found at the bottom of the HHS press release.

From the Rx coverage front, STAT News tells us

Nearly a dozen of the highest-rated hospitals in the U.S. charged commercial health insurers and cash-paying patients significantly more than what Medicare has recently paid for 10 infused medicines on which the government spends the most money, according to a new analysis.

Median prices exceeded the Medicare Part B payment limit by a low of 169% at Rush University Medical Center in Chicago, while the Mayo Clinic Hospital in Phoenix exceeded the payment limit by 344%. Among cash-paying customers, the prices ranged from 149% of the Medicare payment limit at Rush to 306% at Brigham and Women’s Hospital and Massachusetts General Hospital, both based in Boston.

The Part B infused medicines for which Medicare Part B spent the most money were Rituxan, Orencia, Enbrel, Prolia, Eylea, Opdivdo, Keytruda, Avastin, Lucentis, Neulasta, and Remicade, but the list did not include biosimilar versions. These medications are variously used to treat conditions including cancer, rheumatoid arthritis, and macular degeneration.

Medicare Part B already sets Part B drug prices which tend to be injectables administered at facilities. Democrat legislators in Congress also want Medicare Part D to fix prices for certain drugs distributed by pharmacies. Government price fixing has never worked successfully in the American economy in the FEHBlog’s understanding.

Also from the healthcare pricing front, Health Payer Intelligence informs

Outcomes-based contracts continue to be popular for certain therapies as healthcare costs mount, an Avalere study found.

Avalere’s findings draw on survey responses from 51 insurers and pharmacy benefit managers. Altogether, the survey participants cover approximately 59 million members. The survey was fielded from September 27 to October 8, 2021 and it is Avalere’s fifth annual survey on the subject.

“OBCs typically include an agreement between health plans and drug or device manufacturers that ties product reimbursement to specific clinical, quality, or utilization outcomes,” Avalere researchers explained.

Let’s go.

Weekend update

Lincoln Memorial in the Fall

The Senate is on a State work break this week which includes the Veterans’ Day holiday on Thursday. The House of Representatives is not holding votes this week but a handful or so of Committee hearings are scheduled for Tuesday and Wednesday.

Roll Call tells us that

Buoyed, finally, by forward movement on a larger package of President Joe Biden’s domestic priorities, the House late Friday cleared a Senate-passed bipartisan infrastructure bill that pours billions of dollars into roads, bridges, water systems, transit and broadband.

The long-awaited House vote sends the bill, which passed the Senate in August, to Biden for his signature. 

The House vote was 228-206, with 13 Republicans backing it despite GOP leadership whipping against the bill. All but six Democrats voted for the measure, despite the House not voting in tandem on the larger budget reconciliation package as progressives had demanded for months. 

Instead, Democrats were forced to accept a vote to adopt the rule that sets debate parameters on the reconciliation bill as a sign of progress on that measure. 

Under that rule, the House is expected to vote on the social spending / climate budget reconciliation bill during the week of November 15. The additional week is expected to allow the Congressional Budget Office to release its report on this massive spending bill

With respect to the infrastructure bill the Wall Street Journal explains that ‘

The $1 trillion package would invest in refurbishing aging roads, bridges and ports; easing transportation bottlenecks; replacing harmful lead pipes; expanding internet access; upgrading the nation’s power grid; and boosting infrastructure resilience amid growing concerns over climate change. The spending is to be paid for with a variety of revenue streams, including more than $200 billion in repurposed funds originally intended for coronavirus relief but left unused; about $50 billion from delaying a Trump-era rule on Medicare rebates; and $50 billion from certain states returning unused unemployment insurance supplemental funds.

From the COVID vaccine mandate front, the Wall Street Journal reports that the U.S. Court of Appeals temporarily stated the OSHA vaccination screening program rule applicable to private sector employers with 100 or more employees plus the Postal Service.

A three-judge panel on the New Orleans-based Fifth U.S. Circuit Court of Appeals granted an emergency stay prohibiting enforcement of the rules for now, saying they raise “grave statutory and constitutional issues.” The Fifth Circuit said it would quickly consider whether to issue an injunction against the vaccine and testing requirements, ordering the Biden administration to file initial legal papers by late Monday afternoon.

OSHA issued this emergency rule under a law providing that challenges to such rules should be brought in the U.S. Court of Appeals rather than the lower District Courts. That’s a quicker path to Supreme Court review.

Roll Call discusses federal government contractor concerns about legal risks arising from the unclear federal vaccine mandate. The Federal Acquisition Regulation implementing the President’s executive order is still weeks away. In the meantime, contractors have to rely on the Safer Federal Workforce Task Force’s subregulatory FAQs. The Task Force typically issues new FAQs on a weekly basis.

From the Delta variant front, the American Medical Association discusses the available evidence on the utility of COVID booster mixing and matching which the Food and Drug Administration recently authorized.

In other vaccine news, Precision Vaccines reports on a Lancet study on the high value of HPV vaccine:

The Lancet published a review of the UK’s national human papillomavirus (HPV) vaccination program and its positive impact on cervical cancer and grade 3 cervical intraepithelial neoplasia incidence.

Published on November 3, 2021, this observational study shows the use of HPV vaccines dramatically reduces cervical cancer rates by almost 90% in women in their 20s who were offered the vaccine beginning at age 12.

These researchers estimated that the HPV vaccination program prevented around 450 cervical cancers and about 17,200 cases of precancerous conditions over 11 years.

HPV vaccination was most effective when given between the ages of 11 and 13 when someone is less likely to have been exposed to HPV.

“It’s a historic moment to see the first study showing that the HPV vaccine has and will continue to protect thousands of women from developing cervical cancer,” stated Michelle Mitchell, Cancer Research UK’s chief executive, in a related press statement.

The HPV vaccine when administered to boys protects against male cancers according to the CDC’s website. “The U.S. FDA has approved different types of HPV vaccines listed on this Precision Vaccinations webpage.”

Last but not least tomorrow is the opening day for the Federal Employees Benefits Open Season for 2022. Here’s a link to today’s FedWeek report on the big day. “There will be 275 [FEHB] plan choices—down by one after a few dropouts and additions—including 18 nationwide plan choices open to all, four available only to certain groups, and the rest available regionally.” December 13 is the closing day of this Open Season.

Thursday Miscellany

From the Delta variant vaccine front, The American Hospital Association informs us that

  • The Centers for Medicare & Medicaid Services today issued an interim final rule requiring COVID-19 vaccinations for workers in most health care settings, including hospitals and health systems, that participate in the Medicare and Medicaid programs. The rule is effective Nov. 5. Under the regulation, all eligible workers must be fully vaccinated by Jan. 4, 2022.
  • Also this morning, the Occupational Safety and Health Administration (“OSHA”) issued an emergency temporary standard requiring all employees at private businesses with 100 or more workers to be vaccinated by Jan. 4 or get tested for COVID-19 weekly.

The Society for Human Resource Management (SHRM) provides us with SHRM’s Top Takeaways from the OSHA ETS:

  • Employees must be fully vaccinated by January 4, 2022, and employers must require unvaccinated employees to mask and produce a negative test on at least a weekly basis.
  • Employers are required to have a written vaccination policy.
  • The OSHA ETS does not apply to employees who do not report to a workplace where there are other individuals such as coworkers or customers are present; employees working from home; or employees who work exclusively outdoors.
  • The OSHA ETS does not require employers to provide or pay for tests.
  • Employers must pay employees for the time it takes to get vaccinated.
  • Employers must ensure all unvaccinated employees are masked.
  • Employers must report COVID-19 fatalities and hospitalizations to OSHA.
  • The OSHA ETS reaffirms that employers must provide reasonable accommodations.
  • According to the Department of Laborvaccine, testing and face-covering requirements preempt inconsistent state and local requirements.

Closer to home, the OSHA ETC does not apply to workplaces subject to EO 14042 on Requiring Coronavirus Disease 2019 Vaccination for Federal Contractors. However, Govexec points out that

“Under the [Occupational Safety and Health Act], the U.S. Postal Service is treated as a private employer,” said OSHA’s emergency temporary standard, set to officially publish in the Federal Register on Friday. “It is therefore required to comply with this [emergency temporary standard] in the same manner as any other employer covered by the act.” 

The [Labor Department] spokesperson added that there are about 500,000 postal workers and confirmed that the rule applies to all of them.

Federal New Networks adds that

The Biden administration on Thursday pushed back the deadline for federal contractors to comply with its vaccine mandate.

Contractors now have until Jan. 4, 2022, the same deadline the White House set for private sector companies with 100 employees or more to comply with vaccine and testing requirements from the Labor Department’s Occupational Safety and Health Administration. * * *

The White House said it will not apply the OHSA emergency temporary standard or the CMS rule to workplaces subject to the federal vaccine mandate for contractors, so employers won’t have to track multiple requirements.

While federal contractors now have the same Jan. 4 deadline as other private sector companies, there’s a key difference between the two policies.

Under the new OSHA standard, companies with 100 employees or more have to ensure their workers have received either one or both shots by Jan. 4 — or tests for COVID-19 at least weekly.

Under the federal vaccine mandate for contractors, employees don’t have the option to be tested weekly, at least not at this point.

Govexec reports that “The Office of Personnel Management on Wednesday reminded agencies that they must grant federal employees administrative leave to accompany their children to get the COVID-19 vaccine, following the news that more children are now able to get vaccinated.” It would be helpful if OPM gave direct guidance to FEHB carriers on the contractor vaccine mandate.

From the Delta variant front, STAT News reports that

Britain granted conditional authorization on Thursday to the first pill shown to successfully treat Covid-19 so far. It also is the first country to OK the treatment from drug maker Merck, although it wasn’t immediately clear how quickly the pill would be available.

The pill was licensed for adults 18 and older who have tested positive for Covid-19 and have at least one risk factor for developing severe disease, such as obesity or heart disease. Patients with mild-to-moderate Covid-19 would take four pills of the drug, known molnupiravir, twice a day for five days.

An antiviral pill that reduces symptoms and speeds recovery could prove groundbreaking, easing caseloads on hospitals and helping to curb outbreaks in poorer countries with fragile health systems. It would also bolster the two-pronged approach to the pandemic: treatment, by way of medication, and prevention, primarily through vaccinations.

Molnupiravir is also pending review with regulators in the U.S., the European Union, and elsewhere. The U.S. Food and Drug Administration announced last month it would convene a panel of independent experts to scrutinize the pill’s safety and effectiveness in late November.

From the preventive care front —

The Associated Press informs us that

A government advisory committee on Wednesday recommended that all U.S. adults younger than 60 be vaccinated against hepatitis B, because progress against the liver-damaging disease has stalled. 

The decision means that tens of millions of U.S. adults — mostly between the ages of 30 and 59 — would be advised to get shots. Hepatitis B vaccinations became standard for children in 1991, meaning most adults younger that 30 already are protected.

“We’re losing ground. We cannot eliminate hepatitis B in the U.S. without a new approach,” said Dr. Mark Weng of the Centers for Disease Control and Prevention.

The Advisory Committee on Immunization Practices voted unanimously to approve the recommendation Wednesday. The CDC’s director, Dr. Rochelle Walensky, must sign off on it before it becomes public policy, but it’s not clear when she will decide.

The American Cancer Society tells us about the proper use of lung screenings to detect cancer in this Lung Cancer Awareness Month.

The Robert Woods Johnson Foundation has updated its report on the state of childhood obesity in our country.

From the healthcare business front —

Fierce Healthcare reports that

Cigna wrapped up third-quarter earnings for major national payers Thursday morning, where it reported $1.6 billion in profit for the quarter.

The results surpassed Wall Street expectations, according to Zacks Investment Research. Cigna also brought in $44.3 billion in revenue in the third quarter, according to the earnings report, which also beat analysts’ projections.

Both figures were up significantly year over year, Cigna said. In the third quarter of 2020, the insurer earned $1.4 billion in profit and brought in $41 billion in revenue. * * *

Due to the results, Cigna raised its guidance and now expects $20.35 in earnings per share for 2021. The insurer expects full-year revenues of $172 billion.

Fierce Healthcare also catalogs “new [healthcare M&A] deals that were revealed, closed or called off during the month of October.

In that regard Beckers Payer Issues reports that

UnitedHealth Group and Change Healthcare entered into an amended agreement with the Justice Department not to finalize the healthcare companies’ proposed $13 billion deal until late February.

Four things to know:

1. Under the new timing arrangement, the companies agreed not to consummate their deal before Feb. 22, 2022, according to Change Healthcare’s Nov. 3 earnings report. 

2. The new date amends a previous timing agreement announced in August, under which, UnitedHealth and Change agreed to wait at least 120 days after certifying compliance with the Justice Department’s request for more information. Both organizations had agreed to not certify compliance with the request before Sept. 15, meaning the 120 days would have expired in January 2022.

3. The organizations announced the proposed acquisition in January. Change shareholders approved the deal despite backlash from hospital groups arguing that the proposed combination is anticompetitive. 

4. On March 24, the Justice Department issued a second information request to the organizations. In the Nov. 3 earnings report, Change Healthcare shared that it and UnitedHealth “certified substantial compliance” with the second request.

Also STAT News provides a “progress report on Big Retail’s ambitions in health care.” This point impressed the FEHBlog

[T]he physical assets of retail players stand to give them a substantial leg up in parts of the country not already saturated by startups and other rivals, including the Midwest and broad swaths of the South.

“Most people in America live close to some of these retail giants and not to a health care provider,” said Gadelrab, who visited a Walmart for the first time to get tested for Covid-19.

Even for retailers’ significantly buzzier rivals, such as hybrid care startups Carbon Healthand women’s care-focused Tia, physical locations have remained a core part of their business models amid the pandemic, pitting their offerings somewhat against the services offered by Walmart, in particular.

“For us, the physical experience has been around making preventive health something women want to engage in before something is wrong,” said Carolyn Witte, Tia’s co-founder and chief executive officer.

That physical proximity could prove especially useful, Gadelrab said, as parts of the U.S. health care system begin to shift away from a fee-for-service treatment model to one based on value-based or preventive care, since it could theoretically allow retail giants to keep more consistent tabs on patients, much in the same way popular telehealth tools check in regularly with their users. At the same time, retailers also maintain reams of data on consumer health and wellness spending, and more recently, vaccination status — information that could be used to better inform their health care offerings or reach more potential clients.

Midweek Update

From the Delta variant front, MedPage Today reports on a recent study supporting the FDA/CDC conclusion that all immunocompromised folks over the vaccine eligibility age should receive a COVID vaccine booster.

Kaiser Health News surveys the U.S. market for convenience COVID testing.

FedWeek reminds us that

Just days remaining before the deadline for federal employees to receive a Coronavirus vaccination under the mandate and disciplinary actions could soon follow, although indications are that such actions will not necessarily be immediate nor fast-moving.

Taking into account the two-week waiting period afterward that required to be considered fully vaccinated by the deadline of November 22, employees would need to receive either the single Johnson and Johnson vaccine or the second dose of the two-dose Pfizer or Moderna vaccines no later than next Monday (November 8).

In the third quarter financial results department, we find

Healthcare Dive reporting that

  • “CVS Health’s payer business Aetna reported higher-than-expected costs for COVID-19 treatment and testing in the third quarter as the highly infectious delta variant spread and deferred care returned.
  • “However, a greater volume of vaccinations and COVID-19 tests (along with pharmacy services growth) fueled a sharp jump in profit, leading the Woonsocket, Rhode Island-based company to boost its full-year outlook.
  • “CVS beat Wall Street expectations on both earnings and revenue for the quarter, with a topline of $73.8 billion, up 10% year over year, contributing to net income of $1.6 billion, up 30% year over year.”

Fierce Healthcare reporting

  • “Humana expects its individual Medicare Advantage membership to grow by 8% in 2022 as part of a more conservative financial outlook. 
  • “The insurer gave hints to its outlook for next year as part of its earnings report released Wednesday that saw Humana post a $1.5 billion profit in the third quarter but cut its financial outlook for 2021 due in part to higher-than-expected COVID-19 costs.
  • “The insurer’s third-quarter earnings report, though, released Wednesday, pointed to strong growth in its Medicare Advantage offerings and lower-than-expected healthcare use among MA beneficiaries.
  • “Humana also generated $20.7 billion in revenue for the third quarter, which fell short of Wall Street expectations.”

BioSpace reporting

  • “Pfizer reported its third-quarter 2021 financials, citing $24.1 billion in quarterly revenues, a stunning 130% operational growth. If you exclude the sales of its COVID-19 vaccine with BioNTech, revenues grew 7% operationally to $11.1 billion. The company raised its full-year guidance to range from $81 to $82 billion.
  • “’While we are proud of our third quarter financial performance, we are even more proud of what these financial results represent in terms of the positive impact we are having on human lives around the world,’ said Albert Bourla, Pfizer’s chairman and chief executive officer. ‘For example, more than 75% of the revenues we have recorded up through third-quarter 2021 for Comirnaty have come from supplying countries outside the U.S., and we remain on track to achieve our goal of delivering at least two billion doses to low- and middle-income countries by the end of 2022 — at least one billion to be delivered this year and one billion near year, with the possibility to increase those deliveries if more are placed by these countries for 2022.’”

The FEHBlog also ran across this STAT News article discussing Moderna’s unexpected approach to breaking into the CRISPR gene editing market.

Moderna, flush with cash thanks to its blockbuster Covid-19 vaccine, made waves back in August when CEO Stéphane Bancel declared the company’s next frontier to be genome editing, the nascent science of rewriting DNA to treat disease. Three months later, Moderna has picked a partner for its foray into CRISPR, and it’s not one of the field’s multibillion-dollar players.

Metagenomi, a three-year-old startup out of the University of California, Berkeley, signed a deal to help Moderna discover and develop genome-editing therapies, the companies said Tuesday. The agreement includes an up-front cash payment to Metagenomi, bonuses for meeting development milestones, and royalties on any products that arise from the collaboration. Moderna will also make an equity investment in the company. Neither side disclosed financial details.

The idea behind Metagenomi is mining nature’s infinite complexity in search of new ways to edit DNA. That means scouring the natural world for soils, sediments, and microbiomes, putting the samples through intensive genome sequencing, and sifting the results for better genome-editing mousetraps. It’s a process called metagenomics, according to company co-founder and CEO Brian Thomas, and it has already produced results.

Many genome-editing efforts rely on pairing CRISPR with an enzyme called Cas9, which functions as the molecular pair of scissors that makes cuts to DNA. By studying nature, Metagenomi has discovered newer and potentially more potent enzymes that might broaden CRISPR’s medicinal promise.

Cool.

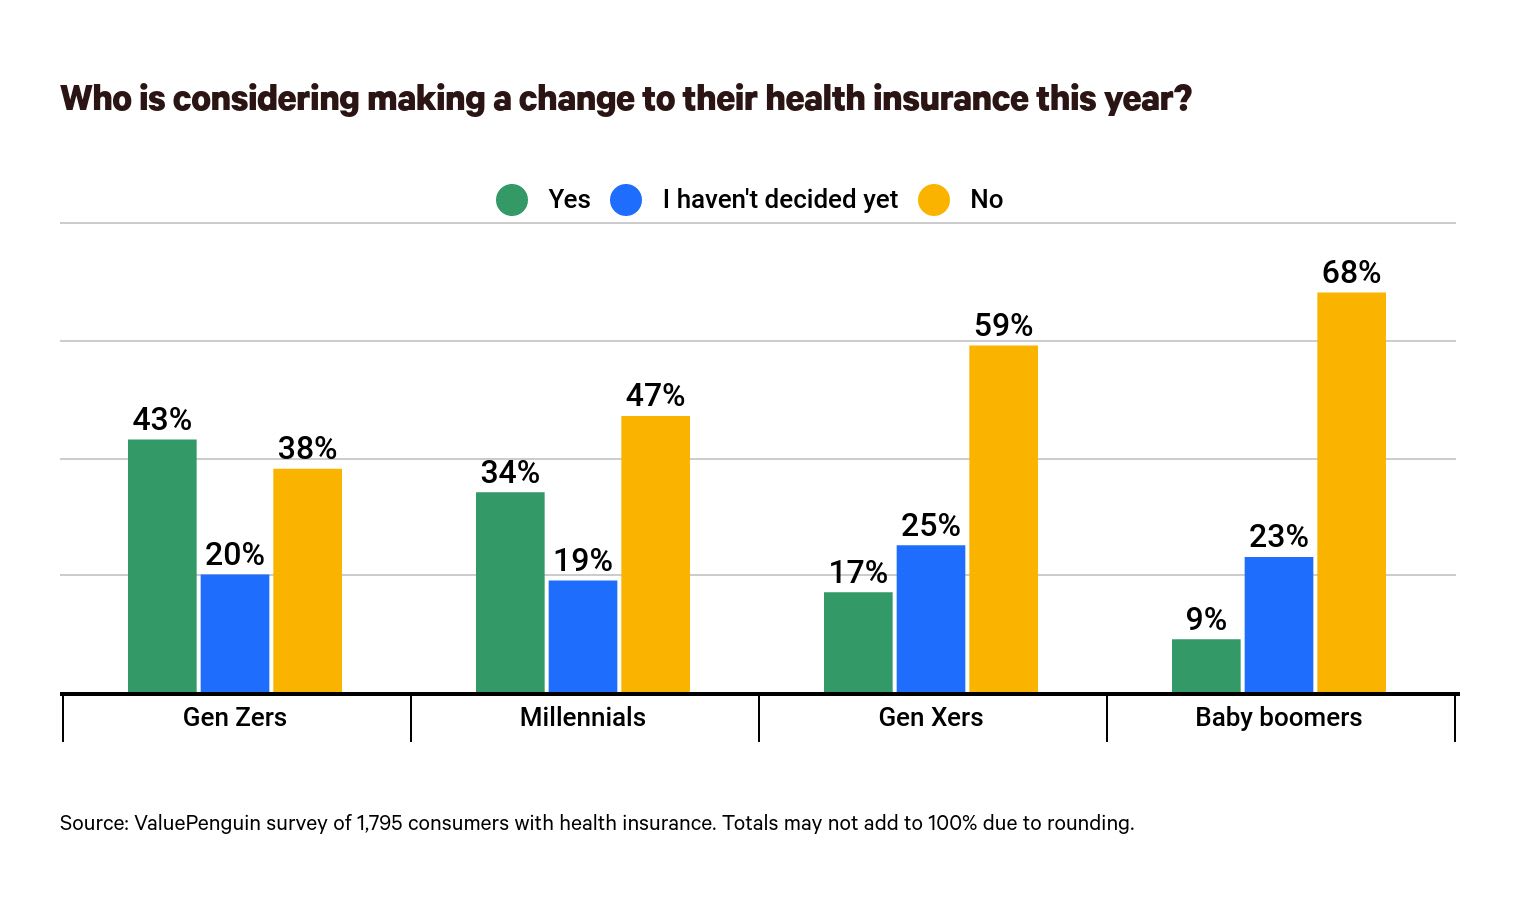
From the Open Season front, Health Payer Intelligence directed the FEHBlog to this fascinating ValuePenguin study of consumer attitudes toward health benefit open seasons. For example, eagerness to consider changing plans steadily decreases with age which may explain the relatively low turnover rate that typically occurs in FEHB Open Seasons.

Who is planning to change their health insurance?
From the ValuePenguin study

EHR Intelligence reports that the federal government is putting its weight behind the adoption of The HL7 Gender Harmony Logical Model in U.S. electronic health record systems:

  • “Gender identity (GI): an individual’s personal sense of being a man, woman, boy, girl, or something else.
  • “Sex for clinical use: a summary sex classification element based on clinical observations like organ survey, hormone levels, and/or chromosomal analysis.
  • “Recorded sex or gender (RSG): sex values or gender values that are specified administrative documents such as identity cards or insurance cards.
  • “Name to use (NtU): the name that the patient wishes to use in healthcare interactions.
  • “Pronouns: the English language third-person personal pronoun determined by the patient for use in healthcare interactions, clinical notes, and written instructions to caregivers.”

Assuming the model works with EHR system, it would be a logical next step to extended this model to health plan claim and customer service systems.

Tuesday Tidbits

From the Delta variant vaccination front, AHIP informs us that

Photo by Patrick Fore on Unsplash

Today, the Centers for Disease Control and Prevention’s (CDC) Advisory Committee on Immunization Practices (ACIP) met to discuss the safety, efficacy and clinical considerations for the Pfizer-BioNTech COVID-19 vaccine in children aged 5-11 years. The committee unanimously voted (14-0) to recommend the vaccine with the following statement:

“The Pfizer-BioNTech COVID-19 vaccine is recommended for children 5-11 years of age in the U.S. population under the FDA’s Emergency Use Authorization (EUA).”

During the meeting, representatives from Pfizer and the CDC presented data that showed the vaccine to be immunogenic and safe, with majority of adverse events documented as injection site pain. Data from Pfizer showed no correlation of the vaccine with incidence of multisystem inflammatory syndrome MIS-C, and the CDC will continue to monitor the long-term effects of myocarditis in this population. The CDC also noted the disparities in COVID-19 disease epidemiology, that Black, Hispanic, and American Indian/Native Alaskan children are at greater risk for hospitalization and disease severity.  * * *

Additionally, the American Academy of Pediatrics, American Academy of Family Physicians, National Association of Pediatric Nurse Practitioners, and the Pediatrics Infection Disease Society endorsed the COVID-19 vaccine’s administration in all eligible children as authorized by the FDA.

The Wall Street Journal adds that the CDC Director Dr. Rochelle Walensky has ratified the ACIP’s recommendation.

The endorsement * * * on Tuesday, was the last step before doctors, nurses and pharmacists could start giving the shots. Some sites could start administering the vaccine as early as Wednesday, though federal officials don’t expect vaccinations in the age group to be in full swing across the U.S. until next week.

Over 2/3rds of the vaccine eligible U.S. population (12 years and older) are fully vaccinated and a quarter of Americans over age 65 have received a booster according to today’s CDC update.

From the also busy Medicare front, the American Hospital Association tells us about three final Calendar Year 2022 rules released today:

— Hospital Outpatient Services (Part A): The Centers for Medicare & Medicaid Services late today issued a final rule that increases Medicare hospital outpatient prospective payment system rates by a net 2.0% in calendar year 2022 compared to 2021.  In addition, as urged by AHA, CMS finalized its proposals to reverse two policies finalized in CY 2021. The first policy halts the elimination of the inpatient only list and adds back to the IPO list almost all of the services removed in 2021. The second reinstates several patient safety criteria for adding a procedure to the ambulatory surgical center covered procedures list that were in place in CY 2020 and prior. The rule also removes 255 of the 258 surgical procedures that had been added to the ASC CPL in 2021.

— Hospital Price Transparency: CMS also finalizes as proposed a number of modifications to the hospital price transparency rule, including significant increases to the civil monetary penalty for noncompliance. * * * Currently, the CMP is set at a maximum amount of $300/day. CMS will scale up the CMP based on a hospital’s bed count, with a minimum of $300/day for small hospitals (30 or fewer beds) and an additional $10/bed/day for larger hospitals with a daily cap of $5,500. CMS also will prohibit specific barriers to accessing the machine-readable files, including through automated searches and direct downloads. CMS provides updated clarifications on the price estimator tools for those hospitals that choose to use them to fulfill the shoppable service requirement, including allowing patients to manually input their insurance information and permitting broad disclaimers, as appropriate.

— Home Healthcare Services (Part A): The Centers for Medicare & Medicaid Services today released its calendar year 2022 final rule for the home health prospective payment system. The rule finalized a net update of 3.2% relative to CY 2021. This includes a 2.6% market basket increase ($465 million), a 0.7% increase for high-cost outlier cases ($125 million), and 0.1% decrease to rural payments as required by law (-$20 million).

— Physician Services (Part B): The Centers for Medicare & Medicaid Services late today released its calendar year 2022 final rule for the physician fee schedule. The rule cuts the conversion factor to $33.59 in CY 2022, as compared to $34.89 in CY 2021, which reflects the expiration of the CY 2021 3.75% payment increase, a 0.00% conversion factor update, and a budget neutrality adjustment. The rule also finalizes several policies to expand access to telehealth for mental health services, including, in certain instances, covering audio-only services. In addition, as urged by the AHA, CMS finalized a delayed implementation of the payment penalty phase of the Appropriate Use Criteria program to the later of Jan. 1, 2023, or the Jan. 1 that follows the end of the COVID-19 public health emergency. Currently, the penalty phase is set to begin Jan. 1, 2022.   “The AHA applauds today’s ruling by CMS to delay the proposed enforcement of the Appropriate Use Criteria (AUC) program as well as to expand access to telehealth for behavioral health services,” said AHA Executive Vice President Stacey Hughes. 

Speaking of telehealth, Healthcare Dive calls attention to its finding that ‘While women are more likely than men to visit doctors and consume healthcare services in general, telehealth seems to be uniquely attractive to women.” Moreover, [t]he data also suggests female physicians offer virtual care services at higher rates than their male counterparts.”

In the tidbits department, we find

  • Healthcare Dive reports that “The median change in operating margins for hospitals fell 18.2% in September compared to August, according to the latest monthly report from Kaufman Hall, a hospital consultant group. Patient volumes declined in almost every key category, including emergency room visits and operating room minutes, potentially signaling that the rise in the delta variant caused some to once again defer care out of concern over contracting the coronavirus. Outpatient revenues declined, too, further underscoring this potential trend. Although fewer patients were admitted, patients were sicker and stayed longer. The average length of stay is also trending above pre-pandemic levels.”
  • MedPage Today offers an interesting story on Chicago’s Rush Medical Center “journey to health equity” using social determinants of health data, among other tools.
  • Federal Times reports that “The Partnership for Public Service held its annual Samuel J. Heyman Service to America awards Nov. 1, honoring nine federal employees and their associated teams out of 29 nominees for making a significant impact through their public service.” Congratulations to all of the nominees and thanks for your service to our country.

Monday Roundup

Photo by Sven Read on Unsplash

From the Delta variant front, Medscape informs us that

“Unvaccinated people who had a recent infection were five times more likely to be reinfected with the coronavirus compared to those who were fully vaccinated and didn’t have a prior infection, according to a new study published Friday in the CDC’s Morbidity and Mortality Weekly Report.”

and

People who already have had COVID-19 may have more reason to get vaccinated, with new findings suggesting that vaccination after infection can boost protection. Under viral threat, the body first uses B cells to make antibodies against the invader, a process that can take up to 2 weeks. The immune system simultaneously creates memory B cells that can recognize the virus if it reappears and rapidly mounts a powerful secondary response.

In a series of  shots, the first dose triggers the primary response. The follow-up doses activate the memory B cells, strengthening defenses against the pathogen.

These new results, published in Cell Reports , show that a SARS-CoV-2 infection, like a first vaccine dose, will elicit the primary response, as expected.

Fierce Biotech tells us that

COVID-19 testing newcomer Detect aims to reset expectations for regular screening against the pandemic coronavirus—and it’s now received an FDA green light to move forward with its rapid, lab-quality test for repeated use in the home.

The company’s molecular diagnostic received an emergency authorization allowing it to be sold at retail stores over-the-counter. Equipped with a reusable analyzer and $50 cartridge-based tests, the system aims to produce results with PCR-level accuracy within one hour.

From the Delta variant mandate front, the Society for Human Resource Management reports that

​The White House issued guidance on Nov. 1 that its Dec. 8 deadline for federal contractors to be vaccinated against COVID-19 isn’t set in stone, providing companies with the opportunity to educate workers past that date rather than fire workers who haven’t been vaccinated by then.

“A covered contractor should determine the appropriate means of enforcement with respect to its employee at a covered contractor workplace who refuses to be vaccinated and has not been provided, or does not have a pending request for, an accommodation,” according to the guidelines.

As federal contractors prepare to implement the vaccine mandate, many questions have arisen on timing, costs and related issues, which prompted the White House to release the new guidance.  

Also today, OMB’s Office of Information and Regulatory Affairs concluded its review of the OSHA vaccination screening rule for private sector employers with 100 or more employees. This means that the rule should be released this week. Heavens only knows when the FAR Council will release its vaccine mandate rule for federal contractors.

Federal News Network offers an update on the federal employee vaccine mandate.

From the recognition department, Fierce Healthcare names ten women of influence in healthcare while Healthcare Dive points out that “Healthcare employees bore the brunt of the pandemic in the workforce. Women bore the brunt of the pandemic at home. Most nurses are both.”

In Affordable Care Act new, the IFEBP reports that “The Internal Revenue Service (IRS) issued the final 1094-B, 1095-B, 1094-C, and 1095-C forms that employers, plan sponsors and group health insurers will use to report health coverage to plan members and the IRS as required by the Affordable Care Act (ACA). IRS hasn’t released final instructions.” Links to the final forms are available at this link.

Weekend update

Thanks to ACK15 for sharing their work on Unsplash.

Happy Halloween!

The U.S. House of Representatives and the Senate will be engaged in floor voting and Committee business this coming week. The Hill brings us up to date on Democrat Congressional leadership negotiations over the social spending budget reconciliation bill. Bloomberg adds

While the $500 billion infrastructure bill has already passed the Senate, the larger economic package will have to return there for another vote. Some Democratic Senators are signaling they may seek changes to what is passed in the House, possibly adding further delays. 

From the Open Season front, the ACA marketplace open season resumes tomorrow. The Federal Employee Benefits Open Season begins a week from tomorrow. OPM’s 2022 online FEHB Plan Comparison Tool is now available.

From the Delta variant front, the Wall Street Journal tells us that

The Food and Drug Administration is delaying a decision on Moderna Inc.’s application to authorize use of its Covid-19 vaccine in adolescents to assess whether the shot leads to a heightened risk of myocarditis, the company said.

The FDA notified Moderna on Friday evening that an analysis may not be completed until January of next year while the agency reviews recent international data on the risk of myocarditis after vaccination, the company said Sunday.

The Wall Street Journal reported earlier this month that the FDA was delaying a decision on Moderna’s application for authorization in 12- to 17-year-olds after several Nordic countries limited use due to myocarditis reports. 

Moderna also said it would delay asking the FDA to authorize use of a lower dose of its shot in even younger children, ages 6 to 11, while the agency continues to review its request to clear the shots in adolescents.

From the CMS front, Medicare offers coverage for those under age 65 who are afflicted with End Stage Renal Disease (“ESRD”). On Friday, CMS finalized its ESRD prospective payment rule for calendar year 2022. In its announcement CMS explained that

Through the ESRD Prospective Payment System (PPS) annual rulemaking, CMS is making changes to the ESRD Quality Incentive Program (QIP) and the ESRD Treatment Choices (ETC) Model, and updating ESRD PPS payment rates. The changes to the ETC Model policies aim to encourage dialysis facilities and health care providers to decrease disparities in rates of home dialysis and kidney transplants among ESRD patients with lower socioeconomic status, making the model one of the agency’s first CMS Innovation Center models to directly address health equity.

“Today’s final rule is a decisive step to ensure people with Medicare with chronic kidney disease have easy access to quality care and convenient treatment options,” said CMS Administrator Chiquita Brooks-LaSure. “Enabling dialysis providers to offer more dialysis treatment options for Medicare patients will catalyze better health outcomes, greater autonomy and better quality of life for all patients with kidney disease.”

That makes sense to the FEHBlog.

From the healthcare network front, the Yale School of Public Health (YSPH”) informs use that “a new survey analysis from a researcher at the YSPH suggests that privately insured adults are significantly more likely to rate their mental health provider network as inadequate compared to their medical provider network.” With due respect to Yale, this finding is hardly surprising given the fact that relative few mental health therapists join a health plan network because they don’t need patient referrals. That’s why it so important for the hub and spoke telehealth services to offer ongoing mental health care over their networks.

From the OPM front, Federal News Network reports that

As agencies contemplate and continue to plan for the future of work, the Office of Personnel Management is trying to let agencies know they have some help — and some new resources — to guide them through the unknown.

The agency is preparing to release more guidance on telework and remote work “very soon,” OPM Director Kiran Ahuja said in an interview with Federal News Network.

It’s all part of an effort to help agencies establish themselves as model employers that can meet the moment — and part of OPM’s own plans to reestablish itself as a human capital resource for the rest of government. They’re priorities Ahuja set in the early days since becoming OPM director, and they’ll continue well into 2022 and beyond, she said.

The guide will offer, in some detail, advice for agencies on making the shift to remote and hybrid work.

“We want to support what’s involved in our lives around flexibilities and child care but also knowing that we can be really productive,” Ahuja said. “We have this guide coming out. We’re also pulling together trainings and information around how to manage in a hybrid work environment and how to operate well in a work environment, as well as a new website focused on future of work.”

Friday Stats and More

Based on the Centers for Disease Control’s COVID Data Tracker, here’s the FEHBlog weekly chart of new COVID cases in 2021, which uses Thursday as the first day of the week:

Encouraging, n’est-ce pas?

The CDC’s chart of new COVID hospitalizations points in the same hopeful direction.

Here’s the FEHBlog’s weekly chart of new COVID deaths which while a lagging indicator is now heading in the right direction too.

Here is the FEHBlog’s weekly chart of newly distributed and administered COVID vaccines, which includes boosters.

For the each of the past three days over 1 million COVID vaccines have been administered in our country. 67.7% of Americans over age 12 (the current minimum age to receive the vaccination) are fully vaccinated. 85% of the 65 and older U.S. population is fully vaccinated and 22% of that cadre has received the booster.

Here is a link to the CDC’s weekly interpretation of these COVID statistics which was released today. The CDC’s most recent Fluview report is that “Seasonal influenza activity in the United States remains low.”

In related Delta variant news, the Washington Post reports that the acting Food and Drug Commissioner Dr. Janet Woodcock today ratified the FDA vaccinations panel’s recommendation to award emergency use authorization to administering the Pfizer vaccine to children ages 5 to 11. The Post explains that

the process of getting vaccines cleared for younger school-age children has been fraught, with members of the FDA’s outside advisory committee expressing some angst and disagreements during a vociferous public debate this week. In the end, the panel voted 17 to 0, with one abstention, to recommend the vaccine, agreeing with the FDA that the shot’s known and potential benefits outweighed the known and potential risks — the criteria for an emergency authorization.

The discussion about the shot is expected to resume Tuesday when the Advisory Committee on Immunization Practices, which advises the Centers for Disease Control and Prevention, is scheduled to meet to recommend how to use the vaccine. After CDC Director Rochelle Walensky signs off, probably on the same day, providers, including pediatricians and pharmacists, will be able to begin administering the vaccine.

The Wall Street Journal adds that

Covid-19 was over five times more common among hospitalized people who were unvaccinated and had a previous infection, compared with those who were fully vaccinated and hadn’t had Covid-19 before, a study published by the Centers for Disease Control and Prevention found.

The report, released Friday and written by scientists from the federal agency as well as hospitals across the U.S., adds to the body of research suggesting that vaccines provide stronger protection against the coronavirus than prior-infection immunity.

In No Surprises Act news, the Texas Medical Association has filed a lawsuit against the federal agencies implementing this law, including OPM, alleging that the recently issued interim final rule on the independent dispute resolution process conflicts with Congressional intent by giving health plans an unfair advantage in NSA arbitrations. The FEHBlog views this as an exercise in futility, but we shall see if the Court share the FEHBlog’s viewpoint.

Also from the litigation front, Govexec reports that

Eleven states with Republican governors are challenging the Biden administration’s vaccine mandate for federal contractors between two lawsuits filed on Thursday and Friday. 

The state of Florida filed a lawsuit in the U.S. District Court for the Middle District of Florida in the Tampa Division seeking an injunction on the mandate that has a December 8 deadline for millions of employees of federal contractors to get vaccinated against COVID-19. Then on Friday, Missouri, Nebraska, Alaska, Arkansas, Iowa, Montana, New Hampshire, North Dakota, South Dakota and Wyoming filed a similar lawsuit in the U.S. District Court for the Eastern District of Missouri also seeking an injunction. 

The FEHBlog will be keeping an eye on these cases too.

Thursday Miscellany

Photo by Josh Mills on Unsplash

The FEHBlog was particularly struck by an in-depth article in the Wall Street Journal about a lower income man in his sixties who emptied his retirement plan to pay for hospital bills for his wife who was stricken with cervical cancer. How does this happen in the Affordable Care Act world. The FEHBlog is not blaming the law. Rather the FEHBlog believes that people from the hospital, the insurance company, etc. dropped the ball when they had a chance to help this now broken man. The woman’s adult daughter, presumably the man’s step daughter, created a Go Fund Me page. Isn’t that a red flag?

The Journal also reports from Capitol Hill that the President’s Hail Mary pass to score a legislative victory with the billion dollar infrastructure bill fell short.

The Mercer consulting company is offering a report on furious state legislative efforts this year to regulate prescription benefit managers in the wake of last December’s U.S. Supreme Court decision on ERISA preemption and such laws, which was favorable to the state legislatures. The laws in the FEHBlog’s view while well intentioned mainly raise administrative costs.

Govexec in an Open Season related article discusses the No Surprises Act provisions that take effect on January 1, 2022, for enrollees with primary FEHB coverage in the United States. The FEHBlog does expect that this law will achieve its objective of getting patients out of the middle of billing disputes between out of network providers and health plans in emergency care, ancillary care at hospitals and surgicenters and air ambulances. The article notes that “The new rules don’t apply to people with coverage through programs such as Medicare, Medicaid, the Indian Health Service, the Veterans Affairs health system or TRICARE, because these programs already have other protections against high medical bills.”

From the third quarter financial reporting front / telehealth front, Healthcare Dive tells us that

  • “Teladoc plans to take on financial risk for its offerings in the future, including its virtual-first primary service, in a bid to expand revenue per member, the CEO of the New York-based virtual care giant said Wednesday.
  • The telehealth vendor made that program, called Primary360, available nationwide earlier this month, and it will be available through CVS Health-owned payer Aetna and Centene’s marketplace plans in Michigan, Mississippi, South Caroline and Texas early next year. And Teladoc is also beginning to talk with health systems about using Primary360 as a white-labeled digital front door to care for their populations, CFO Mala Murphy told investors on a call.
  • In its third quarter financial results also released Wednesday, Teladoc beat Wall Street expectations on earnings and revenue, with a topline of $522 million, up 81% year over year due to strength in multi-product sales and behavioral health, management said. The 19-year-old vendor saw 3.9 million visits in the quarter, representing 37% year-over-year growth.”

From the Affordable Care Act front, Kaiser Health News reports that

The federal government’s effort to penalize hospitals for excessive patient readmissions is ending its first decade with Medicare cutting payments to nearly half the nation’s hospitals.

In its 10th annual round of penalties, Medicare is reducing its payments to 2,499 hospitals, or 47% of all facilities. The average penalty is a 0.64% reduction in payment for each Medicare patient stay from the start of this month through September 2022. The fines can be heavy, averaging $217,000 for a hospital in 2018, according to Congress’ Medicare Payment Advisory Commission, or MedPAC. Medicare estimates the penalties over the next fiscal year will save the government $521 million. Thirty-nine hospitals received the maximum 3% reduction, and 547 hospitals had so few returning patients that they escaped any penalty.

Here is a link to KHN’s online tool to look up hospitals to find out whether the hospital was assessed a 2022 penalty.

From the reports and studies department —

  • The Kaiser Family Foundation released its COVID vaccine monitor for October 2021.
  • The American Medical Association discusses a study concluding that, notwithstanding a tremendous amount of consolidation between health systems and providers, private practices continue to play a “big part” in primary care, which the FEHBlog finds reassuring.
  • Health Payer Intelligence informs us

From the beginning, it was clear that seniors’ lives would be turned upside down as a result of the coronavirus pandemic, but Humana’s survey of over 1,000 seniors reveal the severe toll the pandemic has taken on senior mental health and social health.

“Health plans should take particular notice, since it is critical to understand all the evolving needs of seniors – health, social and behavioral – as the industry increasingly moves toward models of ‘whole health’ senior care and coverage,” said Kathy Driscoll, senior vice president and chief nursing officer at Humana.

The survey reached 1,003 Americans ages 64 and older, nationwide. Kelton Global fielded the survey from September 14 to September 21, 2021.

One of the most striking results of the survey was that, despite the rise in mental and behavioral healthcare needs and the expanded access to telemental and telebehavioral services that the pandemic brought, only three percent of seniors had accessed mental healthcare.

The results run parallel with a separate Anthem study which found that mental healthcare claims dropped even though mental healthcare demand rose during the coronavirus pandemic.

However, the low rate of telehealth utilization for these specific demands does not mean that seniors were as hesitant to use telehealth for other health-related purposes. Seniors were far more likely to use telehealth in order to access wellness programming (84 percent) and a third of seniors used telehealth to connect with their providers.